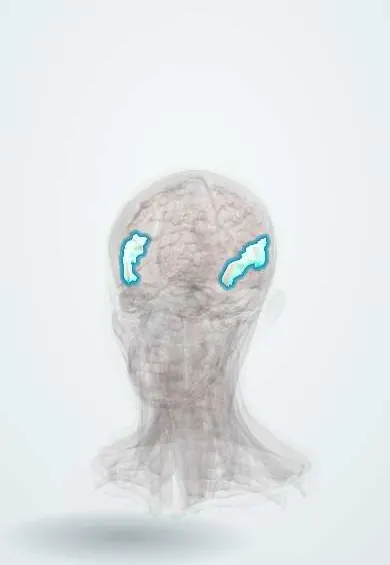
Nervous system · Head and neck
Wernicke's area !
Wernicke's area is at the back of the upper temporal lobe, usually on the left; it understands spoken words, and damage gives fluent but meaningless speech.
Official name: Superior temporal gyrus
Opens in the Durgical app, no sign-up needed.
What it is
The superior temporal gyrus; its back part on the left is Wernicke's area.
What it does
Understands spoken words; damage gives fluent but meaningless speech (receptive aphasia).
Key facts
- Where
- Posterior superior temporal gyrus, usually left
- Blood supply
- MCA inferior division
- Function
- Language comprehension (area 22)
Relations
- In front
- Auditory cortex (transverse temporal gyri of Heschl), which feeds it sound
- Behind
- Angular gyrus, needed for reading and writing
- Above
- Planum temporale and the lateral sulcus; above and behind, the supramarginal gyrus
- Below
- Superior temporal sulcus and the middle temporal gyrus
- Deep
- Arcuate fasciculus, curving around the end of the lateral sulcus to the frontal lobe; below it, the optic radiation (Meyer loop)
How to find it
It is the back third of the superior temporal gyrus of the dominant hemisphere, where the lateral sulcus ends and turns up. On axial and sagittal MRI it lies on the planum temporale, the flat upper surface of the temporal lobe behind the auditory cortex.
Examination
- Comprehension: one-step, then multistep commands and yes/no questions; failure despite fluent speech fits Wernicke aphasia
- Repetition of a phrase: impaired in Wernicke and conduction aphasia, preserved in the transcortical aphasias
On imaging
MRI, in axial and sagittal views, shows the back of the superior temporal gyrus and the planum temporale. In sudden receptive aphasia, DWI shows an infarct in the inferior division territory of the middle cerebral artery; CT can be normal in the first hours, and CT angiography looks for the blocked branch. Before nearby surgery, functional MRI locates language.
Clinical notes
- Transcortical sensory aphasia: fluent speech and poor comprehension but preserved repetition, from lesions in the border zone between the middle and posterior cerebral arteries
- Language mapping during awake surgery protects it when a tumour or an epileptic focus lies nearby
Anatomical variants
- Texts differ on its exact limits; some include the supramarginal and angular gyri
- The planum temporale is usually larger on the left, more clearly in right-handers (some texts)
- Right-sided or bilateral language occurs in a minority, more often in left-handers
Test yourself
Think of the answer, then tap the question to see it.
Where is Wernicke's area?
The back third of the superior temporal gyrus of the dominant (usually left) hemisphere, on the planum temporale behind the auditory cortex.
What are the features of Wernicke (receptive) aphasia?
Fluent speech at a normal rate but full of paraphasias and neologisms, with poor comprehension and poor repetition; the person is often unaware.
Why can Wernicke aphasia be mistaken for confusion or psychiatric illness?
There is usually no weakness (inferior division of the middle cerebral artery) and the person is often unaware; a right upper quadrant field cut may coexist.
Which aphasia comes from damage to the arcuate fasciculus between Wernicke's and Broca's areas?
Conduction aphasia: fluent speech and good comprehension, but repetition fails.
Educational information, not medical advice. For any symptom, see a health professional.
Its names
- Official Latin (TA2)
- gyrus temporalis superior TA2 5489
- Official Spanish (DeCS)
- Área de Wernicke DeCS D065813
- English (TA2)
- Superior temporal gyrus
Related
Sources: Terminologia Anatomica (TA2); DeCS; Neuroanatomy, Wernicke Area.
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.