Conditions · Obstetrics and gynecology
Primary ovarian insufficiency !
Primary ovarian insufficiency is when the ovaries stop working normally before age 40, causing missed periods, low oestrogen and fertility problems.
Updated 2026-11-01
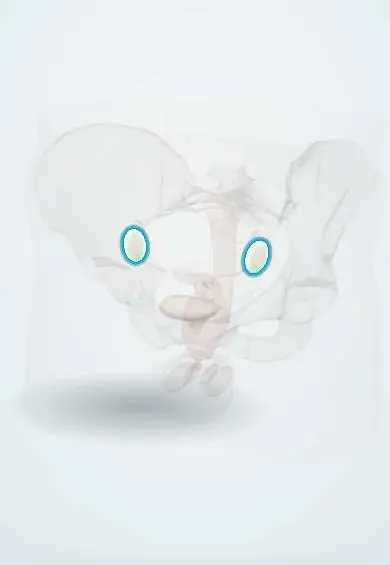
Structures involved
Tap one to see what it is and open it in 3D.
Why it happens
- Sex chromosome disorders: Klinefelter and Turner
- Nonclassic inheritance: repeat expansions, mitochondrial genes, imprinting, mosaicism
- Oogenesis, follicles and ovulation
- Trinucleotide repeat expansion disorders
- Ovary: follicles, ovulation and corpus luteum
What it is
Loss of normal ovarian function before 40 years of age, with oligomenorrhoea or amenorrhoea, raised gonadotropins and low oestradiol. Unlike menopause, ovarian function can fluctuate and occasional ovulation and pregnancy are possible.
Who gets it
Affects roughly 1 in 100 women under 40 and fewer under 30. In most women no cause is found. It is an important cause of secondary amenorrhoea and of primary amenorrhoea in Turner syndrome.
Causes
- Idiopathic (most cases)
- Chromosomal: Turner syndrome (45,X and mosaics) and other X chromosome abnormalities
- Genetic: FMR1 premutation (fragile X carrier)
- Autoimmune: associated with autoimmune thyroid disease, adrenal insufficiency and type 1 diabetes
- Iatrogenic: chemotherapy (alkylating agents), pelvic radiotherapy, ovarian surgery
- Metabolic and infectious: galactosaemia, mumps oophoritis
Risk factors
- Family history of early menopause or fragile X
- Personal or family autoimmune disease
- Cancer treatment in childhood or adolescence
- Smoking
Pathophysiology
The pool of primordial follicles is too small from birth, is depleted faster than normal, or follicles fail to respond to FSH. Reduced inhibin and oestradiol release the hypothalamic-pituitary axis from negative feedback, so FSH rises to menopausal levels. The resulting oestrogen deficiency produces menopause-like symptoms and, because it occurs years early, a greater cumulative risk to bone and heart.
Symptoms and signs
- Irregular periods or loss of periods
- Primary amenorrhoea and delayed puberty in some (Turner syndrome)
- Hot flushes and night sweats
- Vaginal dryness and reduced libido
- Difficulty conceiving
- Mood changes and poor concentration
Diagnosis
- Clinical
- A woman under 40 with at least 4 months of oligomenorrhoea or amenorrhoea; pregnancy is excluded first.
- Tests
- FSH in the menopausal range on two occasions at least 4 weeks apart, with low oestradiol. Once confirmed: karyotype, FMR1 premutation testing, adrenal (21-hydroxylase) and thyroid antibodies, TSH. Prolactin and TSH help rule out other causes of amenorrhoea. Anti-Müllerian hormone is low.
- Imaging
- Bone densitometry (DXA) at diagnosis; pelvic ultrasound may show small ovaries with few follicles.
Differential diagnosis
- Pregnancy
- Polycystic ovary syndrome
- Functional hypothalamic amenorrhoea
- Hyperprolactinaemia (prolactinoma)
- Thyroid disease
- Asherman syndrome (uterine cause)
Goal of treatment
Replace the missing hormones until the usual age of menopause to protect bone, heart and quality of life, screen for associated conditions, and address fertility and emotional needs.
Treatment
- Medical
- Hormone replacement with oestrogen plus a progestogen (if the uterus is present) until about the average age of natural menopause; combined hormonal contraception is an alternative for some women.
- Procedure
- Assisted reproduction with donated oocytes offers the highest chance of pregnancy; fertility preservation can be offered before gonadotoxic cancer treatment.
- Lifestyle
- Weight-bearing exercise, adequate calcium and vitamin D, not smoking.
- Follow-up
- Periodic thyroid and adrenal screening when autoimmune, bone density follow-up, cardiovascular risk control, and psychological support; genetic counselling for fragile X carriers and their families.
Complications
- Infertility
- Osteoporosis and fractures
- Increased cardiovascular disease
- Adrenal insufficiency (autoimmune cases)
- Depression and anxiety
Prognosis
Ovarian function rarely recovers fully, but intermittent ovulation occurs in some women and a small proportion conceive spontaneously. With hormone replacement until the expected age of menopause, the long-term risks to bone and heart are reduced.
Test yourself
Think of the answer, then tap the question to see it.
What defines primary ovarian insufficiency?
Loss of ovarian function before 40, with at least 4 months of oligo- or amenorrhoea and FSH in the menopausal range on two occasions.
Which two genetic tests are standard once the diagnosis is confirmed?
Karyotype (for Turner syndrome and X abnormalities) and FMR1 premutation testing (fragile X).
Which autoimmune condition must be screened for because it can be life threatening?
Autoimmune adrenal insufficiency, by testing 21-hydroxylase antibodies.
How does primary ovarian insufficiency differ from menopause?
It occurs before 40 and ovarian function may fluctuate, so ovulation and pregnancy are occasionally still possible.
Related conditions
- Menopause and climacteric syndrome
- Turner syndrome
- Female infertility
- Osteoporosis
- Hypothyroidism
- Functional hypothalamic amenorrhoea
- Polycystic ovary syndrome
- Prolactinoma (hyperprolactinaemia)
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Primary Ovarian Insufficiency (MedlinePlus (U.S. National Library of Medicine), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.