Polycystic ovary syndrome !
Polycystic ovary syndrome (PCOS) is a common hormonal disorder with irregular ovulation, excess male hormones and many small ovarian follicles.
Updated 2026-10-29
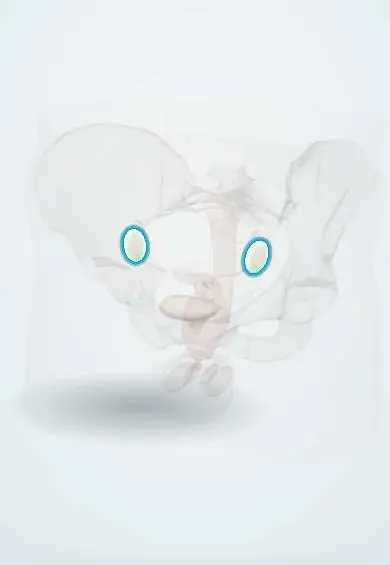
Structures involved
Tap one to see what it is and open it in 3D.
In biochemistry
- Steroid hormone synthesis (overview)
- Leptin, appetite and obesity
- Insulin receptor
- Aromatase (CYP19A1)
- 17α-Hydroxylase/17,20-lyase (CYP17A1)
- 17-Hydroxyprogesterone (17-OHP)
In histology
In embryology
In physiology
- The adrenal cortex: zones, hormones and androgens
- The menstrual cycle: ovary and endometrium
- Testosterone and its actions
- Oogenesis, follicles and ovulation
Why it happens
- Multifactorial (complex) disorders
- Obesity: leptin, adipokines and its consequences
- Islets and insulin: secretion and actions
- Insulin signalling
What it is
A common endocrine and metabolic disorder of reproductive age, defined by combinations of ovulatory dysfunction, androgen excess and polycystic ovarian morphology. Some recent sources use the new name Polyendocrine Metabolic Ovarian Syndrome, which stresses its metabolic side.
Who gets it
One of the most common endocrine disorders in women of reproductive age; prevalence depends on the criteria used. It often starts in adolescence and is under-diagnosed. In Latin America, high rates of obesity and insulin resistance add to its metabolic burden.
Causes
- Polygenic, runs in families
- Insulin resistance with compensatory hyperinsulinaemia
- Faster GnRH pulses that favour LH over FSH
- Developmental factors in utero (proposed)
- Obesity worsens its expression
Risk factors
- Family history of PCOS or type 2 diabetes
- Obesity, especially central
- Insulin resistance
- Premature adrenarche in childhood
Pathophysiology
Rapid GnRH pulses raise LH relative to FSH. LH drives androgen production by theca cells, and relative FSH lack stops follicles maturing, leaving many small arrested follicles. Hyperinsulinaemia boosts ovarian androgens and lowers SHBG, raising free androgens. Without ovulation, the endometrium is exposed to unopposed oestrogen.
Classification
- Rotterdam criteria: at least 2 of 3: ovulatory dysfunction, clinical or biochemical hyperandrogenism, polycystic ovarian morphology (ultrasound or, in adults, raised AMH)
- Other causes must be excluded first (thyroid disease, hyperprolactinaemia, non-classic congenital adrenal hyperplasia, androgen-secreting tumours)
- Phenotypes A–D by which criteria are present; A (all three) carries the greatest metabolic risk
- Adolescents: both ovulatory dysfunction and hyperandrogenism are needed; ultrasound and AMH are not used in the first years after menarche
Symptoms and signs
- Irregular or absent periods
- Hirsutism, acne or androgenic hair loss
- Subfertility from anovulation
- Weight gain and central obesity
- Acanthosis nigricans (sign of insulin resistance)
- More frequent depression and anxiety
Diagnosis
- Clinical
- History of cycles and androgen signs, hirsutism scoring (modified Ferriman–Gallwey), weight, waist, blood pressure and acanthosis nigricans.
- Tests
- Pregnancy test; total and free testosterone; TSH, prolactin and 17-hydroxyprogesterone to exclude mimics; AMH may replace ultrasound in adults; oral glucose tolerance test or HbA1c and lipid profile.
- Imaging
- Transvaginal ultrasound counts follicles and measures ovarian volume (adults only); thresholds depend on equipment and criteria vary.
Differential diagnosis
- Thyroid disease
- Hyperprolactinaemia
- Non-classic congenital adrenal hyperplasia
- Androgen-secreting ovarian or adrenal tumour
- Cushing syndrome
- Functional hypothalamic amenorrhoea
Goal of treatment
Treat what matters most to the patient (cycles, androgen signs, fertility), protect the endometrium and lower long-term metabolic and cardiovascular risk.
Treatment
- Lifestyle
- Healthy eating and physical activity for everyone; modest weight loss in those with excess weight can restore ovulation and improve metabolic risk.
- Medical
- Combined hormonal contraceptives regulate cycles, protect the endometrium and reduce hyperandrogenism; cyclic progestins are an alternative for endometrial protection.
- Medical
- Insulin sensitisers (biguanides) for metabolic features; anti-androgens for hirsutism, only with reliable contraception; cosmetic hair removal.
- Medical
- Ovulation induction for infertility: aromatase inhibitors first line, then gonadotropins or IVF in specialist care.
- Follow-up
- Regular screening for glucose intolerance, dyslipidaemia, hypertension, mood disorders and sleep apnoea.
Drugs for this condition
Complications
- Type 2 diabetes and gestational diabetes
- Dyslipidaemia, metabolic syndrome and higher cardiovascular risk factors
- Endometrial hyperplasia and cancer
- Infertility and pregnancy complications such as preeclampsia
- Obstructive sleep apnoea and fatty liver disease
- Depression, anxiety and body-image distress
Prognosis
A lifelong condition whose features change with age: cycle and androgen problems often ease towards menopause, while metabolic risk persists. With treatment and follow-up most control their symptoms, and many conceive.
Test yourself
Think of the answer, then tap the question to see it.
What are the Rotterdam criteria for PCOS?
Two of three: ovulatory dysfunction, hyperandrogenism and polycystic ovarian morphology, after excluding other causes.
Why does chronic anovulation in PCOS raise the risk of endometrial cancer?
Unopposed oestrogen without cyclic progesterone leads to endometrial hyperplasia.
Which skin sign suggests insulin resistance in PCOS?
Acanthosis nigricans: dark, velvety skin in folds such as the neck and armpits.
Which drug class is first line for ovulation induction in PCOS?
Aromatase inhibitors.
What new name for PCOS appears in some recent sources?
Polyendocrine Metabolic Ovarian Syndrome, which highlights its endocrine and metabolic nature.
Related conditions
- Type 2 diabetes mellitus
- Obesity
- Metabolic syndrome
- Cushing syndrome
- Ovarian cyst
- Endometrial cancer
- Abnormal uterine bleeding
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Polyendocrine Metabolic Ovarian Syndrome (StatPearls (NCBI Bookshelf), 2025).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.