Conditions · Obstetrics and gynecology
Premenstrual syndrome and premenstrual dysphoric disorder !
Premenstrual syndrome is a set of physical and emotional symptoms before periods. Its severe form, PMDD, disrupts work, study and relationships.
Updated 2026-11-01
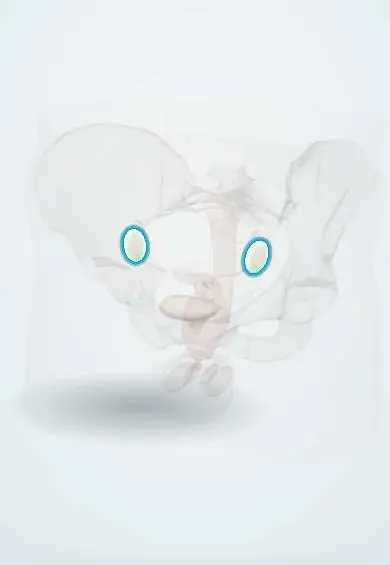
Structures involved
Tap one to see what it is and open it in 3D.
Why it happens
- The menstrual cycle: ovary and endometrium
- Actions of estrogen and progesterone
- The main neurotransmitters
What it is
Premenstrual syndrome (PMS) is a pattern of physical and emotional symptoms that appear in the luteal phase and resolve within a few days of menstruation. Premenstrual dysphoric disorder (PMDD) is its severe form, with predominant mood symptoms that impair functioning, and is classified as a depressive disorder.
Who gets it
Mild premenstrual symptoms are very common in women of reproductive age; clinically significant PMS affects a smaller group, and PMDD a few percent. Symptoms usually begin in the teens or twenties and stop with menopause, pregnancy or suppression of ovulation.
Causes
- Abnormal brain sensitivity to the normal cyclic changes of oestrogen and progesterone
- Altered response to allopregnanolone, a progesterone metabolite that acts on GABA receptors
- Serotonin dysregulation
- Genetic predisposition
Risk factors
- Family history of PMS or PMDD
- Personal history of depression, anxiety or postpartum depression
- Trauma and chronic stress
- Smoking
Pathophysiology
Hormone levels are usually normal; the problem is how the brain reacts to them. After ovulation, rising and falling progesterone and its neuroactive metabolites change GABA and serotonin signalling in mood-regulating areas such as the amygdala and prefrontal cortex. In susceptible women this produces irritability, low mood and anxiety, which disappear when ovulation stops.
Classification
- Premenstrual syndrome (PMS)
- Premenstrual dysphoric disorder (PMDD, DSM-5 depressive disorder)
- Premenstrual exacerbation of another disorder
Symptoms and signs
- Irritability, anger and interpersonal conflict
- Mood swings, sadness or tearfulness
- Anxiety or tension
- Fatigue, poor concentration, sleep changes
- Food cravings or appetite changes
- Breast tenderness, bloating, headache, joint or muscle pain
Diagnosis
- Clinical
- Symptoms confined to the luteal phase, improving within a few days of menstruation and minimal in the week after, confirmed by prospective daily symptom ratings over at least two cycles. PMDD (DSM-5) requires at least five symptoms, at least one of them affective (marked mood swings, irritability, depressed mood or anxiety), with significant distress or dysfunction.
- Tests
- No laboratory test confirms it; TSH and haemoglobin can exclude thyroid disease and anaemia when suggested by the history.
- Imaging
- Not required.
Differential diagnosis
- Major depressive disorder or persistent depressive disorder
- Generalised anxiety disorder
- Bipolar disorder
- Premenstrual exacerbation of another psychiatric or medical condition
- Thyroid disease
- Perimenopause
Goal of treatment
Reduce symptoms and restore daily functioning, starting with education and lifestyle measures and escalating according to severity.
Treatment
- Lifestyle
- Regular aerobic exercise, sleep regularity, stress management, and reducing caffeine, alcohol and salt; symptom diary to track cycles.
- Conservative
- Cognitive behavioural therapy, especially for emotional symptoms.
- Medical
- SSRIs are first-line drug treatment for PMDD and severe PMS, taken continuously or only in the luteal phase; their effect appears faster than in depression.
- Medical
- Ovulation suppression with combined oral contraceptives (for example drospirenone-containing regimens); GnRH agonists with add-back hormones for refractory cases.
- Follow-up
- Screening for suicidal ideation and coexisting mood disorders, and follow-up of response with daily ratings.
Complications
- Impaired work, school and relationships
- Depression and suicide risk in PMDD
- Reduced quality of life
Prognosis
Symptoms tend to recur each cycle until menopause but respond well to treatment; most women with PMDD improve with SSRIs or ovulation suppression.
Test yourself
Think of the answer, then tap the question to see it.
What timing pattern is required to diagnose PMS or PMDD?
Symptoms in the luteal phase that resolve within a few days of menstruation, with a symptom-free interval after menses.
How is the diagnosis confirmed?
With prospective daily symptom ratings over at least two menstrual cycles.
What is first-line drug treatment for PMDD?
SSRIs, given continuously or only during the luteal phase.
Are hormone levels abnormal in PMDD?
No; levels are usually normal, and the disorder reflects abnormal brain sensitivity to normal hormonal changes.
Related conditions
- Major depressive disorder
- Generalized anxiety disorder
- Bipolar disorder
- Persistent depressive disorder (dysthymia)
- Hypothyroidism
- Menopause and climacteric syndrome
- Endometriosis
- Suicidal behaviour and suicide risk
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Premenstrual Syndrome (MedlinePlus (U.S. National Library of Medicine), 2024); Premenstrual dysphoric disorder (MedlinePlus (U.S. National Library of Medicine), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.