Conditions · Obstetrics and gynecology
Amniotic fluid embolism !
A rare, sudden emergency during labour or just after birth: the mother collapses, cannot breathe well and then bleeds because her blood stops clotting.
Updated 2026-11-01
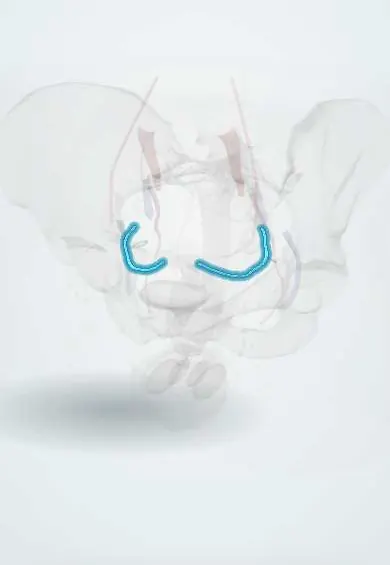
Structures involved
Tap one to see what it is and open it in 3D.
- Uterine veins
- Segmental lung vessels
- Cervix
- Body of uterus
- Pulmonary arteries
- Pulmonary trunk
- Right ventricle
Why it happens
- Shock: types, stages and the organs it damages
- Fat, air and amniotic fluid embolism
- Disseminated intravascular coagulation: how consumption causes both clots and bleeding
- The pulmonary circulation and hypoxic vasoconstriction
- The coagulation cascade
What it is
An unpredictable obstetric catastrophe in which fetal material from the amniotic fluid enters the maternal circulation and triggers an abnormal, anaphylaxis-like response. It presents as the classic triad of sudden hypoxia, hypotension or cardiac arrest, and coagulopathy, usually during labour, caesarean delivery or within about 30 minutes of birth.
Who gets it
Rare: roughly 1 in 20,000 to 1 in 50,000 births. Despite its rarity it is one of the leading direct causes of maternal death in high-income countries, and in Latin America it is a recognised cause of sudden maternal death that is often confirmed only at autopsy. Survival has improved with rapid resuscitation, but many survivors have neurological damage.
Causes
- Breach of the barrier between maternal blood and amniotic fluid (endocervical veins, placental site, uterine tears)
- Abnormal maternal immune and inflammatory response to fetal antigens (mediators such as complement, histamine and tryptase are implicated)
- Not a simple mechanical obstruction: the amount of fetal material does not predict severity
Risk factors
- Caesarean or instrumental delivery
- Induction of labour
- Placental abruption or placenta previa
- Uterine rupture or cervical laceration
- Polyhydramnios and multiple pregnancy
- Maternal age over 35
- Preeclampsia or eclampsia
- Fetal distress
Pathophysiology
Amniotic fluid and fetal cells enter the uterine veins and reach the pulmonary circulation. The release of vasoactive and procoagulant mediators causes intense pulmonary vasoconstriction and acute right-ventricular failure, which produces hypoxia and collapse. Left-ventricular failure and pulmonary oedema follow. Tissue factor in amniotic fluid activates the clotting cascade, leading to disseminated intravascular coagulation with consumption of clotting factors and severe bleeding, typically from the placental site.
Classification
- Phase 1: cardiorespiratory collapse (hypoxia, hypotension, arrhythmia, cardiac arrest)
- Phase 2: haemorrhagic phase with disseminated intravascular coagulation in those who survive the first
Symptoms and signs
- Sudden shortness of breath, restlessness or a sense of impending doom
- Cyanosis and falling oxygen saturation
- Sudden hypotension and shock
- Seizures or loss of consciousness
- Cardiac arrest
- Profuse bleeding from the uterus, wounds and IV sites
- Abrupt fetal bradycardia if the baby is still in the uterus
Diagnosis
- Clinical
- A diagnosis of exclusion made at the bedside: sudden hypoxia, hypotension or arrest, and coagulopathy during labour or soon after birth, without another explanation. Treatment must start before any test result.
- Tests
- Arterial blood gases, complete blood count with platelets, coagulation studies and fibrinogen (low fibrinogen is typical), cross-match, electrolytes, troponin and ECG. Finding fetal squamous cells in maternal pulmonary blood is not diagnostic on its own.
- Imaging
- Bedside echocardiography often shows a dilated, failing right ventricle early on. Chest radiograph may show pulmonary oedema. CT angiography only if stable and thromboembolism must be excluded.
Differential diagnosis
- Pulmonary thromboembolism
- Anaphylaxis
- Septic shock
- Postpartum haemorrhage with hypovolaemic shock
- Eclampsia
- Peripartum myocardial infarction or cardiomyopathy
- Local anaesthetic toxicity or high spinal block
- Air embolism
Goal of treatment
Immediate multidisciplinary resuscitation: restore oxygenation and circulation, deliver the fetus quickly if the mother arrests, and correct the coagulopathy and bleeding.
Treatment
- Acute
- Call for help and start high-quality resuscitation: airway, high-flow oxygen, early intubation and ventilation, and cardiopulmonary resuscitation with manual left uterine displacement if there is cardiac arrest.
- Surgical
- Perimortem caesarean delivery if there is no return of circulation within a few minutes of arrest in a woman beyond about 20 weeks, to improve maternal resuscitation and fetal outcome; hysterectomy if bleeding cannot be controlled.
- Medical
- Vasopressors and inotropes to support the failing right ventricle; pulmonary vasodilators may be used in intensive care.
- Acute
- Massive transfusion protocol with red cells, plasma, platelets and fibrinogen replacement (cryoprecipitate or concentrate), plus antifibrinolytic therapy and uterotonics for atony.
- Follow-up
- Intensive care with invasive blood pressure monitoring, serial coagulation tests, urine output and neurological assessment; nursing priorities are oxygenation, IV access, accurate blood loss measurement and recognising early bleeding.
Complications
- Maternal death
- Hypoxic brain injury
- Disseminated intravascular coagulation and massive haemorrhage
- Acute respiratory distress syndrome
- Acute kidney injury and multiorgan failure
- Peripartum hysterectomy and loss of fertility
- Fetal hypoxic injury or death
Prognosis
Mortality remains high, although most patients now survive with rapid treatment. Many survivors have lasting neurological deficits. Outcome depends on how quickly circulation and oxygenation are restored. Recurrence in a later pregnancy appears to be rare.
Prevention
- It cannot be predicted or prevented
- Preparedness saves lives: obstetric emergency drills, massive transfusion protocols and teams able to perform a perimortem caesarean delivery
Test yourself
Think of the answer, then tap the question to see it.
What is the classic triad of amniotic fluid embolism?
Sudden hypoxia, hypotension or cardiac arrest, and coagulopathy (disseminated intravascular coagulation), during labour or just after delivery.
Which heart chamber typically fails first, as seen on bedside echocardiography?
The right ventricle, from acute pulmonary vasoconstriction and pulmonary hypertension.
Which laboratory finding supports the haemorrhagic phase?
Low fibrinogen with prolonged clotting times and low platelets, consistent with disseminated intravascular coagulation.
What should be done if a pregnant woman beyond about 20 weeks remains in cardiac arrest after a few minutes of CPR?
Perimortem caesarean delivery, while resuscitation continues.
Related conditions
- Disseminated intravascular coagulation
- Postpartum haemorrhage
- Pulmonary embolism
- Anaphylaxis
- Placental abruption
- Uterine rupture
- Eclampsia
- Acute respiratory distress syndrome (ARDS)
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Amniotic Fluid Embolism (Cleveland Clinic, 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.