Acute respiratory distress syndrome (ARDS) !
Acute respiratory distress syndrome (ARDS) is a sudden, widespread lung injury in which the air sacs fill with fluid, causing severe lack of oxygen.
Updated 2026-10-30
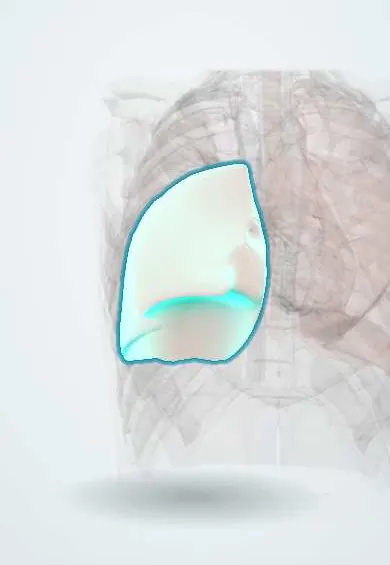
Structures involved
Tap one to see what it is and open it in 3D.
- Right lower lobe
- Left lower lobe
- Segmental lung vessels
- Pulmonary arteries
- Trachea
- Diaphragm
- Right ventricle
In biochemistry
Microorganisms that cause it
In histology
In the clinical exam
In physiology
- The alveolar gas equation and the A–a gradient
- Ventilation–perfusion matching and West zones
- The causes of hypoxemia
- Oxygenation: SpO₂, PaO₂, cyanosis and oxygen therapy
- Lung and chest wall compliance
- Surface tension, surfactant and Laplace's law
- Physiology of pulmonary edema
- Hypoxemic and hypercapnic respiratory failure
Why it happens
- Vascular changes in acute inflammation: vasodilation, leakage, exudate vs transudate
- When leukocytes injure tissue: proteases, oxidants and NETs
- How septic shock develops
- Shock: types, stages and the organs it damages
What it is
Acute, diffuse inflammatory lung injury with leaky alveolar capillaries, causing non-cardiogenic pulmonary oedema and severe hypoxaemia. It is triggered by a direct lung insult or a systemic illness.
Who gets it
A common reason for mechanical ventilation in intensive care, and many cases go unrecognised. Sepsis and pneumonia are the leading causes; COVID-19 greatly increased cases in Latin America. In five ICUs in Lima, Peru, 31% of 1,657 mechanically ventilated adults had ARDS at some point, with a 90-day mortality of 55–56%.
Causes
- Direct lung injury: pneumonia (including viral), aspiration, lung contusion, inhalation injury, near-drowning
- Indirect injury: sepsis (the most common cause), major trauma, acute pancreatitis, multiple transfusions, burns
- Drug overdose and some drug reactions
Risk factors
- Sepsis
- Severe pneumonia
- Chronic alcohol use
- Shock
- Major trauma and multiple transfusions
- Older age
Pathophysiology
Inflammation damages the alveolar epithelium and capillary endothelium, so protein-rich fluid floods the alveoli and hyaline membranes form (diffuse alveolar damage). Surfactant loss collapses alveoli, causing shunt and stiff lungs. An exudative phase is followed by a proliferative phase and, in some patients, fibrosis.
Classification
- Berlin definition severity, by PaO2/FiO2 with PEEP of at least 5: mild (200–300), moderate (100–200), severe (100 or less)
- Direct (pulmonary) or indirect (extrapulmonary) cause
- A newer global definition also includes patients on high-flow oxygen and uses oxygen saturation
Symptoms and signs
- Rapidly worsening breathlessness and tachypnoea
- Hypoxaemia that responds poorly to oxygen
- Diffuse crackles
- Signs of the trigger (fever, shock, trauma)
Diagnosis
- Clinical
- Berlin definition: onset within one week of a known insult or new respiratory symptoms; bilateral opacities not fully explained by effusion, collapse or nodules; respiratory failure not fully explained by heart failure or fluid overload.
- Tests
- Arterial blood gas for the PaO2/FiO2 ratio; tests for the cause (cultures, lipase); BNP and ECG help rule out cardiogenic oedema.
- Imaging
- Chest X-ray or CT shows bilateral opacities; echocardiography helps exclude heart failure; lung ultrasound is useful at the bedside.
Differential diagnosis
- Cardiogenic pulmonary oedema
- Bilateral pneumonia
- Diffuse alveolar haemorrhage
- Acute exacerbation of interstitial lung disease
- Acute eosinophilic pneumonia
Goal of treatment
Treat the cause, maintain oxygenation while avoiding further ventilator injury to the lungs, and support other organs until the lungs recover.
Treatment
- Medical
- Treatment of the trigger: antibiotics and source control in sepsis, management of pancreatitis or trauma.
- Acute
- Lung-protective ventilation: low tidal volumes calculated from predicted body weight, limited plateau pressure and adequate PEEP.
- Acute
- Prone positioning for many hours a day in moderate to severe ARDS.
- Medical
- Conservative fluid strategy once shock resolves; sedation and, in selected severe cases, neuromuscular blockers; corticosteroids in some settings.
- Procedure
- Extracorporeal membrane oxygenation (ECMO) in experienced centres for refractory hypoxaemia.
- Rehabilitation
- Early rehabilitation and follow-up of physical, cognitive and psychological effects after intensive care.
Complications
- Ventilator-associated pneumonia
- Barotrauma and pneumothorax
- Multiorgan failure
- Pulmonary fibrosis
- Intensive care-acquired weakness
- Long-term cognitive and psychological problems
Prognosis
Mortality is high and rises with severity, age and the cause. Many survivors regain near-normal lung function, but weakness, fatigue and psychological problems can last months to years.
Test yourself
Think of the answer, then tap the question to see it.
What are the main criteria of the Berlin definition of ARDS?
Onset within one week, bilateral opacities, respiratory failure not explained by heart failure or fluids, and PaO2/FiO2 of 300 or less with PEEP of at least 5.
What is the most common cause of ARDS?
Sepsis, followed by pneumonia and aspiration.
What is the basic principle of ventilation in ARDS?
Lung-protective ventilation: low tidal volumes based on predicted body weight, limited plateau pressure and adequate PEEP.
Which positioning strategy improves survival in moderate to severe ARDS?
Prone positioning for prolonged periods each day.
What is the typical histological finding in ARDS?
Diffuse alveolar damage with hyaline membranes.
Related conditions
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Acute Respiratory Distress Syndrome (StatPearls (NCBI Bookshelf), 2024); Risk factors for the development of acute respiratory distress syndrome in mechanically ventilated adults in Peru: a multicenter observational study (Critical care (London, England), 2019) · adapted, CC BY 4.0.
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.