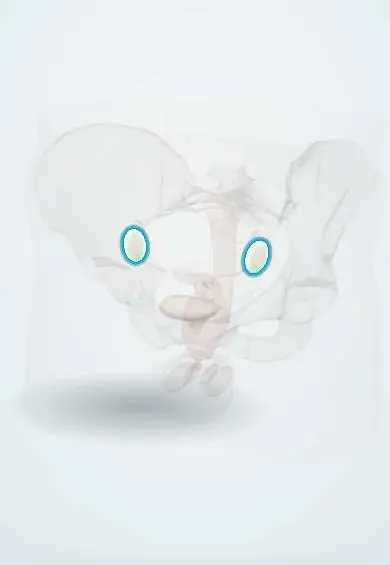
Ovarian cyst !
An ovarian cyst is a fluid-filled sac in or on the ovary; most are linked to the menstrual cycle and go away on their own, and few are cancer.
Updated 2026-10-29
Structures involved
Tap one to see what it is and open it in 3D.
In histology
In embryology
In the clinical exam
In physiology
What it is
A fluid-filled sac in or on the ovary. Most are functional cysts linked to the menstrual cycle that resolve on their own; a smaller share are benign or, rarely, malignant tumours.
Who gets it
Very common in women of reproductive age and often found incidentally on ultrasound. After menopause, cysts are less common and need more careful assessment for malignancy.
Causes
- Follicular cyst: a follicle that fails to rupture at ovulation
- Corpus luteum cyst, which may bleed (haemorrhagic cyst)
- Endometrioma (endometriosis of the ovary)
- Mature cystic teratoma (dermoid cyst)
- Serous or mucinous cystadenoma; rarely a borderline or malignant tumour
Risk factors
- Reproductive age with ovulatory cycles
- Ovulation-inducing fertility treatment
- Endometriosis
- Early pregnancy (corpus luteum cyst)
- Smoking, linked to functional cysts in some studies
Pathophysiology
Functional cysts form when a follicle keeps growing instead of rupturing, or when the corpus luteum fills with fluid or blood. Most regress within a few cycles. Neoplastic cysts arise from the surface epithelium or germ cells and do not regress.
Classification
- Functional: follicular, corpus luteum, haemorrhagic
- Benign neoplastic: dermoid cyst, cystadenoma
- Endometrioma
- Ultrasound risk systems (for example IOTA rules or O-RADS) sort cysts by likely risk of malignancy
Symptoms and signs
- Often no symptoms; found incidentally
- Dull one-sided pelvic pain or pressure
- Bloating or a feeling of fullness
- Menstrual irregularity with some functional cysts
- Sudden severe pain with rupture, bleeding or torsion
Diagnosis
- Clinical
- History, timing in the cycle and pelvic examination; many are found on imaging done for another reason.
- Tests
- Pregnancy test (hCG); complete blood count if bleeding is suspected; CA-125 mainly after menopause or when a mass looks complex, knowing it also rises in benign conditions.
- Imaging
- Transvaginal ultrasound is the main test: a simple thin-walled cyst is almost always benign; solid parts, papillae or blood flow raise concern. MRI helps with indeterminate masses.
Differential diagnosis
- Ectopic pregnancy
- Hydrosalpinx or tubo-ovarian abscess
- Paraovarian cyst
- Pedunculated uterine fibroid
- Ovarian cancer
Goal of treatment
Tell benign from suspicious cysts, relieve symptoms, prevent complications such as torsion, and preserve ovarian tissue.
Treatment
- Follow-up
- Watchful waiting with repeat ultrasound for simple cysts, which usually resolve within a few cycles.
- Medical
- Analgesics for pain; combined hormonal contraceptives may reduce new functional cysts but do not shrink existing ones.
- Surgical
- Laparoscopic cystectomy for persistent, large, symptomatic or complex cysts, preserving the ovary where possible.
- Acute
- Emergency surgery for torsion or rupture with ongoing bleeding.
Complications
- Ovarian torsion
- Rupture with haemoperitoneum
- Chemical peritonitis from a ruptured dermoid cyst
- Reduced ovarian reserve after repeated surgery
Prognosis
Functional cysts usually resolve without treatment. Benign neoplastic cysts are cured by removal, though endometriomas and dermoid cysts can recur.
Test yourself
Think of the answer, then tap the question to see it.
What is the most common type of ovarian cyst in women of reproductive age?
A functional follicular cyst, which usually resolves on its own within a few cycles.
Which ultrasound features suggest an ovarian mass may be malignant?
Solid components, papillary projections, thick septa, strong internal blood flow and ascites.
Do combined hormonal contraceptives make an existing functional cyst disappear faster?
No. They may prevent new functional cysts but do not speed the resolution of existing ones.
Which ovarian cyst may contain hair, fat and teeth?
The mature cystic teratoma (dermoid cyst).
Why is CA-125 less useful before menopause?
It also rises in benign conditions such as endometriosis, fibroids, menstruation and pelvic infection.
Related conditions
- Ovarian torsion
- Polycystic ovary syndrome
- Endometriosis
- Ovarian cancer
- Ectopic pregnancy
- Dysmenorrhoea
- Molar pregnancy (hydatidiform mole)
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Ovarian Cyst (StatPearls (NCBI Bookshelf), 2023).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.