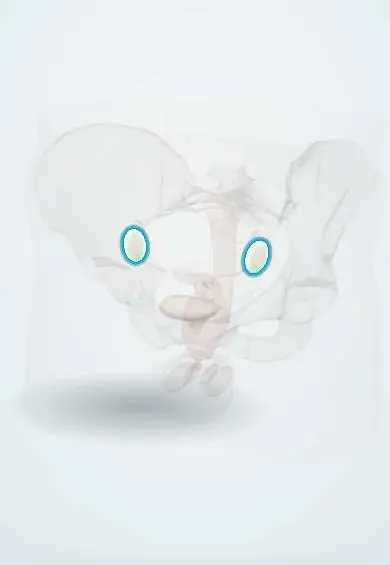
Ovarian torsion !
Ovarian torsion is the twisting of an ovary on its supports, cutting off its blood flow; it causes sudden severe pelvic pain and is a surgical emergency.
Updated 2026-10-29
Structures involved
Tap one to see what it is and open it in 3D.
- Ovaries
- Suspensory ligament of ovary
- Ovarian ligament
- Ovarian artery
- Uterine tubes
- Mesovarium
- Broad ligament
In the clinical exam
In physiology
Why it happens
- Infarction: red vs white, and what decides the damage
- Hypoxia, ischemia and reperfusion injury
- Ovary: follicles, ovulation and corpus luteum
What it is
Partial or complete twisting of the ovary on its supporting ligaments, often together with the uterine tube (adnexal torsion). It cuts off venous and then arterial flow and is a gynaecological surgical emergency.
Who gets it
Seen mostly in women of reproductive age, but also in girls and in pregnancy. It is a classic cause of acute pelvic pain to consider alongside appendicitis and ectopic pregnancy in emergency departments in Colombia and elsewhere.
Causes
- An enlarged ovary that acts as a pivot: functional cyst, dermoid cyst (mature teratoma) or other benign mass
- Ovarian enlargement after ovulation induction (ovarian hyperstimulation)
- Long or lax supporting ligaments, especially in children, who can twist a normal ovary
Risk factors
- Ovarian mass or cyst, mainly benign and of moderate size (larger masses are often cited as a risk)
- Pregnancy, especially the first trimester
- Fertility treatment
- Previous torsion
- Polycystic-appearing ovaries
Pathophysiology
The ovary rotates around the suspensory ligament (with the ovarian vessels) and the ovarian ligament. Thin-walled veins and lymphatics collapse first, so the ovary swells with oedema; arterial inflow then fails and ischaemia and necrosis follow. The right side is affected more often, perhaps because the sigmoid colon limits movement on the left.
Classification
- Partial or intermittent (pain that comes and goes) or complete
- Isolated ovarian, isolated tubal or combined adnexal torsion
- With a normal ovary (more typical in children) or with an ovarian mass
Symptoms and signs
- Sudden, severe, one-sided lower abdominal or pelvic pain, sometimes after exercise or a change in position
- Nausea and vomiting, common
- Earlier episodes of similar pain that settled (intermittent torsion)
- Tender adnexal mass on examination in some patients
- Low-grade fever if necrosis develops
Diagnosis
- Clinical
- Suspected from sudden pelvic pain, vomiting and an adnexal mass. Signs are often non-specific, so a low threshold for surgical review is usual. The diagnosis is confirmed at surgery.
- Tests
- Pregnancy test (hCG) to exclude ectopic pregnancy; complete blood count; urinalysis. Tumour markers only when a mass looks suspicious.
- Imaging
- Pelvic ultrasound with Doppler: enlarged, oedematous ovary, peripheral follicles, an underlying mass, free fluid or a twisted pedicle (whirlpool sign). Normal Doppler flow does not rule torsion out. CT or MRI if the picture is unclear.
Differential diagnosis
- Ectopic pregnancy
- Ruptured or haemorrhagic ovarian cyst
- Acute appendicitis
- Pelvic inflammatory disease or tubo-ovarian abscess
- Ureteric colic (kidney stones)
Goal of treatment
Untwist the adnexa quickly to save the ovary and fertility, and treat the underlying mass.
Treatment
- Acute
- Analgesia, antiemetics and intravenous fluids while emergency surgery is arranged.
- Surgical
- Laparoscopic detorsion; the ovary is usually preserved even if it looks dark, because most recover function.
- Surgical
- Cystectomy for the underlying cyst; oophorectomy only if the ovary is clearly necrotic or a malignancy is suspected, more often after menopause.
- Follow-up
- Follow-up ultrasound to check the ovary and any remaining mass; oophoropexy is considered in selected recurrent cases.
Complications
- Loss of the ovary from necrosis
- Infection or peritonitis from a necrotic adnexa
- Reduced ovarian reserve
- Recurrent torsion
- Pregnancy loss when torsion occurs in pregnancy
Prognosis
With early detorsion most ovaries recover function. Delayed diagnosis increases the chance of losing the ovary.
Test yourself
Think of the answer, then tap the question to see it.
Which vessels are compressed first in ovarian torsion?
The veins and lymphatics, causing oedema and enlargement before the arterial supply fails.
Does normal Doppler flow on ultrasound exclude ovarian torsion?
No. Flow can be present, especially in partial or intermittent torsion; clinical suspicion leads to surgery.
Is a dark, congested ovary removed at surgery for torsion?
Usually not. Detorsion and preservation are preferred because most ovaries recover function.
Which test is done first in any woman of reproductive age with acute pelvic pain?
A pregnancy test, to exclude ectopic pregnancy.
What is the most common predisposing factor for ovarian torsion in adults?
An enlarged ovary from a benign cyst or mass, such as a dermoid cyst or a functional cyst.
Related conditions
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Ovarian Torsion (StatPearls (NCBI Bookshelf), 2023).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.