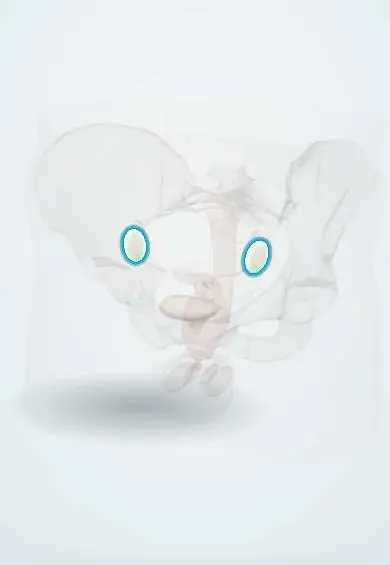
Ovarian cancer !
Ovarian cancer is a cancer of the ovary, uterine tube or peritoneum; the commonest type often starts in the end of the tube and is usually found late.
Updated 2026-10-29
Structures involved
Tap one to see what it is and open it in 3D.
- Ovaries
- Infundibulum and fimbriae
- Rectouterine pouch
- Suspensory ligament of ovary
- Ovarian artery
- External iliac nodes
- Obturator nodes
- Broad ligament
In biochemistry
In histology
Why it happens
- Hereditary cancer syndromes: the table to know
- Tumour suppressor genes: RB, TP53, APC, BRCA and the two-hit hypothesis
- Pathways of spread and the usual metastatic sites
- Tumour markers: serum and tissue, and what each one is for
- Frozen section: the intraoperative consultation
- Genomic instability: mismatch repair, BRCA and xeroderma pigmentosum
Show 1 more
What it is
A malignant tumour of the ovary, the uterine tube or the peritoneum. Most are epithelial cancers, and the commonest, high-grade serous cancer, often starts in the fimbriae of the uterine tube.
Who gets it
Less common than cervical or breast cancer but one of the deadliest gynaecological cancers, because most cases are found at an advanced stage. Risk rises with age and is highest after menopause; it also occurs in Colombia and Latin America, with no reliable screening for women at average risk.
Causes
- Epithelial tumours (most): high-grade serous, low-grade serous, endometrioid, clear cell and mucinous
- Germ cell tumours, mainly in girls and young women
- Sex cord–stromal tumours, which may produce hormones
- Metastases to the ovary, for example from the stomach or colon (Krukenberg tumour)
Risk factors
- Increasing age
- Inherited variants in BRCA1 or BRCA2, or Lynch syndrome
- Family history of ovarian or breast cancer
- Endometriosis (linked to clear cell and endometrioid types)
- Never having been pregnant
Pathophysiology
Many high-grade serous cancers start as precursor lesions in the tubal fimbriae and spread to the ovary and peritoneum. Tumour cells shed into the peritoneal cavity, seed the omentum and peritoneal surfaces and cause ascites. Lymphatic spread goes to pelvic and para-aortic nodes.
Classification
- By histology: epithelial (serous, endometrioid, clear cell, mucinous), germ cell, sex cord–stromal
- Borderline tumours (low malignant potential)
- FIGO stages I–IV: confined to ovary, pelvic spread, peritoneal or nodal spread, distant metastasis
Symptoms and signs
- Persistent bloating or increased abdominal size
- Early satiety or loss of appetite
- Pelvic or abdominal pain
- Urinary urgency or frequency
- Change in bowel habit, weight loss and fatigue in advanced disease
Diagnosis
- Clinical
- Symptoms are vague, so the diagnosis is often delayed. Examination may find a fixed pelvic mass or ascites. Diagnosis is confirmed by histology, at surgery or by biopsy.
- Tests
- CA-125, mainly in postmenopausal women; other markers (such as AFP, hCG, LDH, inhibin) when germ cell or stromal tumours are possible; risk scores combine CA-125, ultrasound and menopausal status. Genetic testing is offered to patients with epithelial cancer.
- Imaging
- Transvaginal ultrasound first; CT of chest, abdomen and pelvis for staging; MRI for indeterminate masses.
Differential diagnosis
- Benign ovarian cyst or cystadenoma
- Endometrioma
- Tubo-ovarian abscess
- Metastasis from gastric or colorectal cancer
- Peritoneal tuberculosis, which can also cause ascites and raised CA-125
Goal of treatment
Remove all visible tumour and control residual disease with systemic therapy, preserving fertility only in selected early cases.
Treatment
- Surgical
- Staging and cytoreductive surgery: hysterectomy, removal of both adnexa, omentectomy and resection of visible disease, ideally by a gynaecologic oncologist.
- Medical
- Platinum-based chemotherapy with a taxane, after surgery or before it (neoadjuvant) when complete removal is not possible at first.
- Medical
- Maintenance with PARP inhibitors or anti-angiogenic agents in selected patients, especially with BRCA variants.
- Follow-up
- Follow-up with symptoms, examination and CA-125; genetic counselling for relatives.
Drugs for this condition
Complications
- Malignant ascites and pleural effusion
- Bowel obstruction
- Venous thromboembolism
- Recurrence after initial response
- Treatment toxicity and surgical morbidity
Prognosis
Survival is high when the cancer is confined to the ovary but falls sharply at advanced stages. Most patients respond to first treatment, but recurrence is common.
Prevention
- Combined oral contraceptive use, pregnancy and breastfeeding are linked to lower risk
- Risk-reducing removal of tubes and ovaries for carriers of BRCA variants, after counselling
- Removal of the tubes (opportunistic salpingectomy) during other pelvic surgery is offered in many centres
Test yourself
Think of the answer, then tap the question to see it.
Where do many high-grade serous ovarian cancers originate?
In the fimbriae of the uterine tube, from precursor lesions in the tubal epithelium.
Why is ovarian cancer usually diagnosed at an advanced stage?
Symptoms such as bloating, early satiety and pelvic pain are vague, and there is no effective screening test for average-risk women.
Which inherited syndromes increase the risk of ovarian cancer?
Hereditary breast and ovarian cancer syndrome (BRCA1/BRCA2) and Lynch syndrome.
What is a Krukenberg tumour?
A metastasis to the ovary, classically from a gastric (or colorectal) cancer, with signet-ring cells.
Which chemotherapy combination is standard first-line treatment for epithelial ovarian cancer?
A platinum agent with a taxane.
Related conditions
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Epithelial Ovarian Cancer (StatPearls (NCBI Bookshelf), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.