Conditions · Pediatrics and neonatology
Prematurity and its complications !
A baby born before 37 weeks has organs that are not ready yet. Lungs, brain, gut and eyes face problems that need special care.
Updated 2026-11-01
Structures involved
Tap one to see what it is and open it in 3D.
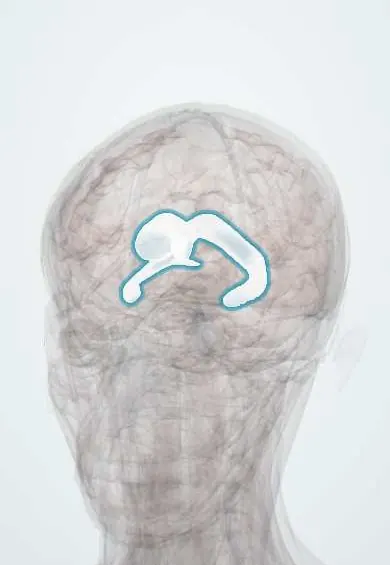
- Lateral ventricles
- Ileum
- Retina
- Choroid plexus
- White matter
- Ligamentum arteriosum
- Right lower lobe
- Left lower lobe
- Cecum
- Ascending colon
In embryology
- Gestational age vs fertilization age: how pregnancy is dated
- Fetal period: month 3 to birth
- Fetal lung, kidney and brain maturation: what preterm birth interrupts
- Patent ductus arteriosus
- Lung development: the five stages
- Surfactant and fetal lung maturity
- Ionizing radiation, tobacco and cocaine
Why it happens
- Prematurity and fetal growth restriction
- Neonatal respiratory distress syndrome: surfactant and hyaline membranes
- Necrotizing enterocolitis: why the premature gut is vulnerable
- Sudden infant death syndrome: what is known
- Newborn physiology and fetal maturation
- Surface tension, surfactant and Laplace's law
What it is
Birth before 37 completed weeks of gestation. The preterm infant's immature organs expose it to a typical set of short- and long-term complications affecting the lungs, brain, gut, eyes, immune system and metabolism.
Who gets it
WHO estimates that about 13.4 million babies were born preterm in 2020, roughly one in ten births, and that complications of preterm birth are the leading cause of death in children under five. Rates vary from about 4% to 16% between countries. In Colombia and Latin America prematurity is a leading cause of neonatal mortality, and kangaroo mother care, a programme first developed in Bogotá, is a key low-cost intervention.
Causes
- Spontaneous preterm labour, with or without infection or inflammation
- Preterm prelabour rupture of membranes
- Medically indicated preterm delivery (pre-eclampsia, fetal growth restriction, placental abruption, placenta praevia)
Risk factors
- Previous preterm birth and short cervix
- Multiple pregnancy
- Maternal infections (urinary, genital, periodontal) and chorioamnionitis
- Hypertensive disorders and diabetes in pregnancy
- Adolescent or older maternal age, short interval between pregnancies
- Smoking, substance use, poor prenatal care and low socioeconomic status
Pathophysiology
Organs that normally mature in the third trimester are not ready: surfactant production is low, the germinal matrix next to the lateral ventricles is fragile, the gut barrier and its blood flow are immature, retinal vessels have not reached the periphery, and immunity, thermoregulation and glycogen and fat stores are limited. Each of these gaps explains one of the classic complications.
Classification
- Extremely preterm: before 28 weeks
- Very preterm: 28 to under 32 weeks
- Moderate to late preterm: 32 to under 37 weeks
- By birth weight: low (under 2,500 grams), very low (under 1,500 grams), extremely low (under 1,000 grams)
Symptoms and signs
- Small size, thin skin with lanugo and little subcutaneous fat
- Weak suck and poor coordination of suck, swallow and breathing
- Breathing pauses (apnoea of prematurity) and periodic breathing
- Hypothermia and difficulty keeping temperature
- Low muscle tone and immature reflexes
- Jaundice that is more frequent and prolonged
Diagnosis
- Clinical
- Gestational age is set by early ultrasound dating or last menstrual period and checked at birth with a maturity score (such as the New Ballard score); weight, length and head circumference are plotted on preterm growth charts.
- Tests
- Glucose, blood gases, bilirubin and blood count as indicated; screening for retinopathy of prematurity by dilated eye examination in at-risk infants; hearing screening; metabolic screening.
- Imaging
- Serial cranial ultrasound to detect intraventricular haemorrhage and periventricular leukomalacia; chest X-ray for respiratory problems; abdominal X-ray if NEC is suspected; echocardiography for a patent ductus arteriosus.
Differential diagnosis
- Small for gestational age term infant (intrauterine growth restriction) rather than preterm
- Incorrect dating of the pregnancy
- Genetic syndromes with low birth weight
Goal of treatment
Support immature organs (breathing, temperature, nutrition), prevent infection and the typical complications, screen for them early, and follow growth and neurodevelopment after discharge.
Treatment
- Acute
- Delivery-room care: delayed cord clamping when possible, heat-loss prevention (plastic wrap, radiant warmer), and CPAP or surfactant for respiratory distress.
- Conservative
- Kangaroo mother care (skin-to-skin contact with exclusive breastfeeding) improves temperature control, breastfeeding and survival in stable preterm infants.
- Medical
- Caffeine for apnoea of prematurity, gradual enteral feeding with human milk plus parenteral nutrition, treatment of PDA, sepsis and anaemia as needed.
- Follow-up
- Nursing care: thermoneutral incubator, cardiorespiratory and saturation monitoring, oxygen targets, infection control, minimal handling, family-centred care; scheduled ROP eye screening, cranial ultrasound and hearing tests.
- Medical
- Before birth: antenatal corticosteroids, magnesium sulphate for neuroprotection in very early preterm birth, antibiotics for preterm prelabour rupture of membranes, and transfer of the mother to a centre with neonatal intensive care.
Complications
- Respiratory distress syndrome, bronchopulmonary dysplasia and apnoea of prematurity
- Intraventricular haemorrhage, post-haemorrhagic hydrocephalus and periventricular leukomalacia
- Necrotising enterocolitis
- Retinopathy of prematurity, which can lead to blindness
- Patent ductus arteriosus
- Sepsis, hypothermia, hypoglycaemia and hyperbilirubinaemia
- Long term: cerebral palsy, learning and behavioural problems, hearing and vision loss
Prognosis
Survival and outcome depend mainly on gestational age, birth weight and access to neonatal intensive care: most late preterm infants do well, while extremely preterm infants have higher mortality and neurodevelopmental impairment.
Prevention
- Quality prenatal care with screening and treatment of infections and hypertensive disorders
- Progesterone or cervical cerclage in selected women with a short cervix or previous preterm birth
- Family planning with adequate spacing between pregnancies
- Stopping smoking and substance use in pregnancy
Test yourself
Think of the answer, then tap the question to see it.
What is the definition of preterm birth?
Birth before 37 completed weeks of gestation.
Where does intraventricular haemorrhage of prematurity usually start?
In the fragile germinal matrix next to the lateral ventricles, usually in the first days of life.
Which methylxanthine is used for apnoea of prematurity?
Caffeine (citrate).
What intervention, first developed in Bogotá, improves survival of stable preterm infants?
Kangaroo mother care: continuous skin-to-skin contact with exclusive breastfeeding.
Which preterm complication is linked to unregulated oxygen and screened by eye examination?
Retinopathy of prematurity.
Related conditions
- Neonatal respiratory distress syndrome (hyaline membrane disease)
- Necrotising enterocolitis
- Neonatal sepsis
- Perinatal asphyxia and hypoxic-ischaemic encephalopathy
- Neonatal hypoglycaemia (including infant of a diabetic mother)
- Patent ductus arteriosus
- Hydrocephalus
- Preeclampsia
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Preterm birth (World Health Organization (WHO), 2023); Premature infant (MedlinePlus (U.S. National Library of Medicine), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.