Conditions · Obstetrics and gynecology
Ovarian hyperstimulation syndrome !
An overreaction of the ovaries to fertility drugs: they swell and fluid leaks into the belly and chest. Severe cases cause clots and kidney injury.
Updated 2026-11-01
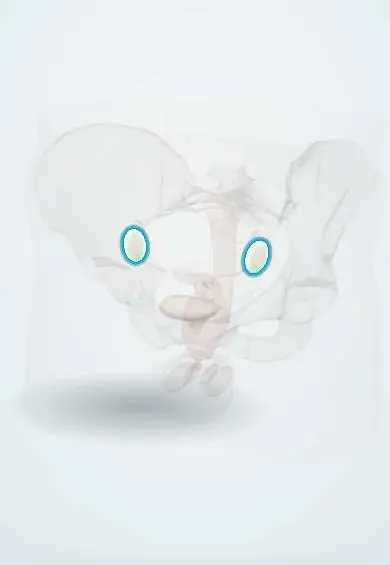
Structures involved
Tap one to see what it is and open it in 3D.
Why it happens
- Edema and effusions: the four mechanisms
- Starling forces at the capillary
- Fluid shifts between compartments
What it is
An iatrogenic complication of ovarian stimulation in assisted reproduction, in which enlarged ovaries release vasoactive mediators that increase capillary permeability, shifting fluid into the third space (ascites, pleural effusion) with intravascular depletion.
Who gets it
Mild forms are common after controlled ovarian stimulation; moderate to severe forms affect a small percentage of in vitro fertilisation cycles. Its frequency has fallen with modern protocols. It appears mainly after ovulation is triggered with hCG and is worse if pregnancy occurs.
Causes
- Gonadotropin stimulation for in vitro fertilisation or other assisted reproduction
- Triggering final oocyte maturation with hCG
- Endogenous hCG from early pregnancy (late-onset form)
- Rarely, clomiphene or letrozole, or spontaneous (multiple pregnancy, hypothyroidism)
Risk factors
- Polycystic ovary syndrome
- Young age and low body weight
- High anti-Müllerian hormone or antral follicle count
- Many developing follicles or rapidly rising oestradiol during stimulation
- Previous ovarian hyperstimulation syndrome
- Pregnancy, especially multiple
Pathophysiology
hCG stimulates the many corpora lutea of hyperstimulated ovaries to release vascular endothelial growth factor (VEGF) and other mediators. These increase capillary permeability, so protein-rich fluid leaves the vessels into the peritoneal and pleural spaces. The intravascular volume falls, causing haemoconcentration (rising haematocrit), reduced renal perfusion with oliguria, and a hypercoagulable state that favours venous and arterial thrombosis. The enlarged ovaries can twist or rupture.
Classification
- Mild: abdominal bloating and discomfort, enlarged ovaries
- Moderate: nausea, vomiting, ultrasound evidence of ascites
- Severe: clinical ascites, hydrothorax, haematocrit above about 45%, oliguria, hyponatraemia, hyperkalaemia
- Critical: tense ascites, acute kidney injury, thrombosis, acute respiratory distress syndrome
- Early onset (within days of the trigger) or late onset (driven by pregnancy hCG)
Symptoms and signs
- Abdominal bloating, distension and pain
- Nausea and vomiting, diarrhoea
- Rapid weight gain
- Reduced urine output
- Shortness of breath
- Leg swelling or calf pain (thrombosis)
Diagnosis
- Clinical
- Symptoms after an ovarian stimulation cycle, with daily weight, abdominal girth, fluid balance and vital signs used to grade severity.
- Tests
- Full blood count (haematocrit, leucocytosis), electrolytes (hyponatraemia, hyperkalaemia), creatinine, liver function, coagulation and serum hCG.
- Imaging
- Pelvic ultrasound showing enlarged multicystic ovaries and ascites; chest radiograph or ultrasound for pleural effusion; Doppler for suspected thrombosis or torsion.
Differential diagnosis
- Ectopic pregnancy
- Ovarian torsion or haemorrhagic cyst
- Pelvic infection or appendicitis
- Heart failure or liver disease (other causes of ascites)
Goal of treatment
Support the circulation and kidneys until the condition resolves spontaneously, prevent thrombosis, and recognise and treat life-threatening complications.
Treatment
- Conservative
- Mild and moderate cases: outpatient care with oral fluids guided by thirst, analgesia (avoiding non-steroidal anti-inflammatory drugs), avoidance of strenuous activity and intercourse, and daily weight.
- Acute
- Severe cases: hospital admission, intravenous crystalloids and albumin as needed, strict fluid balance, and ultrasound-guided paracentesis for tense ascites or breathlessness.
- Medical
- Thromboprophylaxis with low-molecular-weight heparin in moderate to severe cases; diuretics are avoided while intravascular volume is low.
- Follow-up
- Nursing priorities: daily weight, abdominal girth, strict intake and output, vital signs, oxygen saturation and serial haematocrit and electrolytes; intensive care for critical cases.
- Procedure
- Prevention in high-risk cycles: antagonist protocols, GnRH-agonist trigger instead of hCG, and freezing all embryos to avoid pregnancy in that cycle.
Complications
- Venous and arterial thromboembolism
- Acute kidney injury
- Pleural effusion and acute respiratory distress syndrome
- Ovarian torsion or rupture
- Electrolyte disturbance
Prognosis
Most cases are self-limited, resolving within one to two weeks or with the next menstruation; late-onset cases linked to pregnancy last longer. Deaths are rare with good supportive care.
Prevention
- Individualised stimulation dosing, antagonist protocols, GnRH-agonist trigger, cycle cancellation or freeze-all strategy in women at high risk
Test yourself
Think of the answer, then tap the question to see it.
Which mediator is central to the capillary leak in ovarian hyperstimulation syndrome?
Vascular endothelial growth factor (VEGF) released under hCG stimulation.
Why is haematocrit monitored?
Rising haematocrit shows haemoconcentration from fluid leaking into the third space and predicts thrombosis and renal hypoperfusion.
Which two strategies prevent this syndrome in a high-risk IVF cycle?
GnRH-agonist trigger instead of hCG and freezing all embryos (also antagonist protocols).
Which pre-existing condition is the main risk factor?
Polycystic ovary syndrome.
Related conditions
- Female infertility
- Polycystic ovary syndrome
- Ovarian torsion
- Deep vein thrombosis
- Pulmonary embolism
- Pleural effusion
- Acute kidney injury
- Acute respiratory distress syndrome (ARDS)
- Ectopic pregnancy
- Ovarian cyst
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Ovarian hyperstimulation syndrome: MedlinePlus Medical Encyclopedia (MedlinePlus (U.S. National Library of Medicine), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.