Conditions · Pediatrics and neonatology
Intraventricular haemorrhage of prematurity !
Bleeding inside the brain's fluid spaces in babies born very early, usually in the first days of life. Severe bleeds can cause hydrocephalus.
Updated 2026-11-01
Structures involved
Tap one to see what it is and open it in 3D.
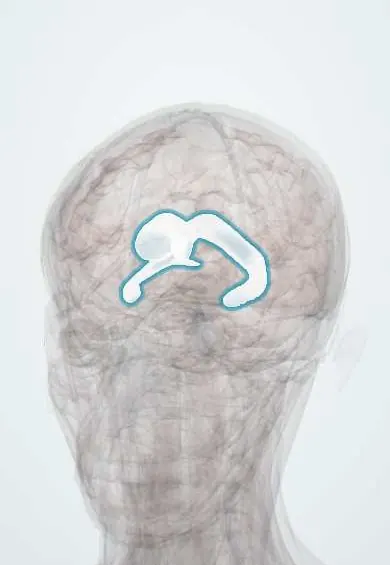
- Lateral ventricles
- Caudate nucleus
- Choroid plexus
- Third ventricle
- Cerebral aqueduct
- Fourth ventricle
- White matter
- Thalamus
Why it happens
- Hemorrhage: petechiae, purpura, ecchymosis, hematoma, and what blood loss does
- Prematurity and fetal growth restriction
- Neonatal respiratory distress syndrome: surfactant and hyaline membranes
- Cerebral blood flow, brain metabolism and intracranial pressure
What it is
Bleeding that starts in the germinal matrix, a fragile vascular zone next to the lateral ventricles over the caudate nucleus, and may spread into the ventricles or brain tissue. It mainly affects babies born before 32 weeks, most often in the first 72 hours of life.
Who gets it
Frequency is inversely related to gestational age; it is most common in extremely preterm and very low birth weight infants. It remains a key cause of neurological disability among preterm survivors in Latin American neonatal units.
Causes
- Rupture of fragile germinal matrix capillaries
- Fluctuating cerebral blood flow with impaired autoregulation
- Venous congestion and raised venous pressure
Risk factors
- Gestational age under 32 weeks and very low birth weight
- No antenatal corticosteroids
- Respiratory distress syndrome, mechanical ventilation and pneumothorax
- Hypotension or rapid fluid boluses, hypercapnia and acidosis
- Perinatal hypoxia, sepsis and coagulopathy
- Outborn birth and transport
Pathophysiology
The germinal matrix is richly vascular but has thin-walled vessels with poor support, and the preterm brain cannot keep flow steady when blood pressure swings. Bleeding begins in the subependymal matrix and may enter the ventricles; a large clot can block venous drainage and cause periventricular hemorrhagic infarction, and blood products can obstruct CSF flow and cause post-hemorrhagic hydrocephalus.
Classification
- Grade I: germinal matrix hemorrhage only
- Grade II: blood in the ventricles without dilation
- Grade III: intraventricular blood with ventricular dilation
- Grade IV (periventricular hemorrhagic infarction): bleeding into the adjacent brain tissue
Symptoms and signs
- Often silent; found on routine cranial ultrasound
- Apnea and bradycardia
- Hypotonia, decreased activity and poor suck
- Pallor and an unexplained fall in hematocrit
- Seizures in larger bleeds
Diagnosis
- Clinical
- Suspected in a very preterm infant with sudden instability; most cases are found by screening.
- Tests
- Hemoglobin and hematocrit, platelets and coagulation tests, blood gases and glucose.
- Imaging
- Cranial ultrasound through the anterior fontanelle is the test of choice for screening and grading, repeated over the first weeks; MRI near term-equivalent age assesses white matter injury.
Differential diagnosis
- Periventricular leukomalacia
- Hypoxic-ischemic encephalopathy
- Neonatal sepsis or meningitis
- Subdural or subarachnoid hemorrhage from birth trauma
- Congenital hydrocephalus
Goal of treatment
Prevent bleeding and its extension by keeping blood flow and gas exchange stable, and detect and manage hydrocephalus early.
Treatment
- Acute
- Supportive care: stable blood pressure and ventilation, avoiding swings in CO2, correcting coagulopathy and anemia, and gentle handling with the head in midline.
- Follow-up
- Serial cranial ultrasound and daily head circumference to detect progressive ventricular dilation.
- Procedure
- Temporary CSF drainage (lumbar or ventricular taps, a ventricular reservoir) for progressive post-hemorrhagic hydrocephalus.
- Surgical
- A ventriculoperitoneal shunt when hydrocephalus persists.
- Rehabilitation
- Early intervention programs, physiotherapy and neurodevelopmental follow-up.
Complications
- Post-hemorrhagic hydrocephalus
- Periventricular hemorrhagic infarction
- Cerebral palsy, especially spastic diplegia or hemiplegia
- Cognitive delay and epilepsy
- Death in severe bleeds
Prognosis
Grade I–II bleeds usually have a good outcome. Grade III and periventricular infarction carry a high risk of hydrocephalus, cerebral palsy and death.
Prevention
- Antenatal corticosteroids and birth in a center with a neonatal intensive care unit
- Delayed cord clamping
- Avoiding rapid fluid shifts and blood-pressure swings in the first days
Test yourself
Think of the answer, then tap the question to see it.
Where does intraventricular hemorrhage of prematurity originate?
In the germinal matrix, the fragile vascular zone beside the lateral ventricles over the caudate nucleus.
Which test is used to screen and grade it?
Cranial ultrasound through the anterior fontanelle.
When does most intraventricular hemorrhage occur?
In the first 72 hours after birth.
What is the main late complication of grade III bleeds?
Post-hemorrhagic hydrocephalus, along with a high risk of cerebral palsy.
Which antenatal measure lowers its risk?
Antenatal corticosteroids given to mothers at risk of preterm birth.
Related conditions
- Prematurity and its complications
- Hydrocephalus
- Cerebral palsy
- Neonatal respiratory distress syndrome (hyaline membrane disease)
- Perinatal asphyxia and hypoxic-ischaemic encephalopathy
- Neonatal sepsis
- Apnoea of prematurity
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Intraventricular hemorrhage of the newborn (MedlinePlus Medical Encyclopedia (U.S. National Library of Medicine), 2025).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.