Community-acquired pneumonia !
Community-acquired pneumonia is a lung infection caught outside hospital, causing fever, cough and breathlessness, with a new shadow on the X-ray.
Updated 2026-10-29
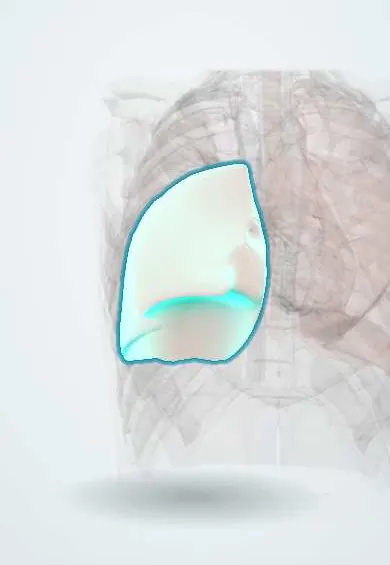
Structures involved
Tap one to see what it is and open it in 3D.
In biochemistry
Microorganisms that cause it
- Human metapneumovirus
- Klebsiella pneumoniae
- Pseudomonas aeruginosa
- Haemophilus influenzae
- Legionella pneumophila
- Streptococcus pneumoniae
- Chlamydia pneumoniae / Chlamydia psittaci
- Mycoplasma pneumoniae
- Influenza virus
In immunology
- Immunity to microbes: which arm defends against what
- Acute-phase response and fever (CRP, ESR, procalcitonin)
- Colombia's PAI schedule (which vaccines, at what age)
In the clinical exam
- Chest palpation: expansion and tactile fremitus
- Chest percussion: resonance, dullness and hyperresonance
- Lung auscultation: normal breath sounds
- Adventitious sounds: crackles, wheezes, rhonchi, stridor and pleural rub
- Voice sounds: bronchophony, egophony and whispered pectoriloquy
- The pleuropulmonary syndromes: the comparison table to know
- Consolidation syndrome
- Respiratory distress and respiratory failure: the signs
- Fever, infection and sepsis: the bedside signs
In physiology
- Ventilation–perfusion matching and West zones
- The causes of hypoxemia
- The pulmonary circulation and hypoxic vasoconstriction
- Hypoxemic and hypercapnic respiratory failure
- Airway defenses, cough and mucociliary clearance
Why it happens
- Outcomes of acute inflammation: resolution, abscess, scar or chronic inflammation
- Patterns of acute inflammation: serous, fibrinous, purulent, abscess, ulcer
- Inflammation: the cardinal signs and its five steps
- How septic shock develops
- Leukocyte recruitment: rolling, adhesion, transmigration, chemotaxis
- Systemic effects of inflammation: fever, acute-phase proteins, leukocytosis, sepsis
What it is
Acute infection of the lung parenchyma acquired outside hospital, with new infiltrate on imaging and symptoms such as fever, cough and breathlessness.
Who gets it
A leading cause of hospital admission and infectious death worldwide, heaviest at the extremes of age. In Colombia and Latin America it is a frequent reason for emergency visits, especially in older adults and in people with chronic lung or heart disease.
Causes
- Streptococcus pneumoniae (most common bacterial cause)
- Haemophilus influenzae and Moraxella catarrhalis (often with COPD)
- Atypical organisms: Mycoplasma pneumoniae, Chlamydophila pneumoniae, Legionella
- Respiratory viruses (influenza, SARS-CoV-2, RSV)
- Staphylococcus aureus and Gram-negative bacilli in selected patients
Risk factors
- Age over 65 or under 5
- COPD, asthma, heart failure, diabetes
- Smoking and alcohol use
- Immunosuppression, including HIV
- Aspiration risk: stroke, impaired swallowing, reduced consciousness
- Recent viral respiratory infection
Pathophysiology
Microorganisms reach the alveoli, usually by microaspiration of oropharyngeal flora or inhalation, and overcome local defences. The inflammatory response fills alveoli with exudate (consolidation), reducing gas exchange and causing hypoxaemia. A systemic response can progress to sepsis.
Classification
- Typical (lobar, often pneumococcal) vs atypical presentation
- Severity by validated scores (e.g. CURB-65, PSI): outpatient, ward or ICU
- Aspiration pneumonia
Symptoms and signs
- Fever and chills
- Cough, often productive
- Shortness of breath
- Pleuritic chest pain
- Crackles, bronchial breathing or dullness over the affected area
- Confusion or falls in older adults, sometimes without fever
Diagnosis
- Clinical
- Compatible symptoms with focal chest signs; severity is graded with CURB-65 (confusion, urea, respiratory rate, blood pressure, age 65 or over) to guide site of care.
- Tests
- Full blood count, urea and electrolytes, inflammatory markers; blood gas or pulse oximetry. In moderate to severe cases, blood and sputum cultures and urinary antigens; viral testing as indicated.
- Imaging
- Chest X-ray confirms a new infiltrate. Ultrasound can show consolidation or effusion; CT is reserved for unclear or complicated cases.
Differential diagnosis
- Acute heart failure
- Pulmonary embolism
- Lung cancer with post-obstructive pneumonia
- Pulmonary tuberculosis
- Acute exacerbation of COPD or asthma
Goal of treatment
Clear the infection with timely, appropriate antibiotics, support oxygenation, choose the right site of care by severity and prevent complications.
Treatment
- Medical
- Empirical antibiotics covering typical organisms, with a macrolide or tetracycline added or chosen for atypical cover, per local guidelines and resistance patterns.
- Medical
- Antivirals when influenza is suspected or confirmed; narrowing antibiotics once cultures are back.
- Follow-up
- Reassessment at 48–72 hours: fever, oxygen needs and ability to take oral treatment.
- Acute
- Oxygen, fluids and, in severe cases, ICU care with ventilatory support and sepsis management.
- Lifestyle
- Smoking cessation and vaccination against pneumococcus and influenza.
Drugs for this condition
- Amoxicillin + clavulanic acid
- Cefepime
- Cefotaxime
- Cefuroxime
- Ceftaroline
- Ertapenem
- Linezolid
- Azithromycin
- Clarithromycin
- Doxycycline
- Erythromycin
- Levofloxacin
- Moxifloxacin
- Tigecycline
- Amoxicillin
- Ceftriaxone
- Pneumococcal vaccine
- Influenza vaccine
Complications
- Parapneumonic effusion and empyema
- Lung abscess
- Sepsis and septic shock
- Respiratory failure and ARDS
- Cardiac events (arrhythmia, myocardial infarction) in older adults
Prognosis
Most outpatients recover within a few weeks, although fatigue and cough can persist. Mortality rises with age, comorbidity and severity scores; ICU patients carry a substantially higher risk.
Prevention
- Pneumococcal and influenza vaccination
- Smoking cessation
- Swallowing assessment and oral hygiene in people at risk of aspiration
Test yourself
Think of the answer, then tap the question to see it.
What are the five components of the CURB-65 score?
Confusion, urea raised, respiratory rate high, low blood pressure, and age 65 or over. Each scores one point; higher totals suggest hospital or ICU care.
Which organism is the most common bacterial cause of community-acquired pneumonia?
Streptococcus pneumoniae (pneumococcus).
Which three atypical organisms commonly cause community-acquired pneumonia?
Mycoplasma pneumoniae, Chlamydophila pneumoniae and Legionella species.
What finding on chest X-ray confirms the diagnosis of pneumonia?
A new pulmonary infiltrate or consolidation, sometimes with air bronchograms, in a patient with compatible symptoms.
Related conditions
- Pleural effusion
- Chronic obstructive pulmonary disease (COPD)
- Sepsis and septic shock
- HIV infection and AIDS
- Pulmonary embolism
- Lung cancer
- Pulmonary tuberculosis
- Bacterial meningitis
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Community-Acquired Pneumonia (StatPearls (NCBI Bookshelf), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.