Conditions · Gastroenterology and hepatology
Zollinger-Ellison syndrome (gastrinoma) !
A gastrin-making tumour, usually in the pancreas or duodenum, drives huge stomach acid output, causing severe, repeated ulcers and diarrhoea.
Updated 2026-11-01
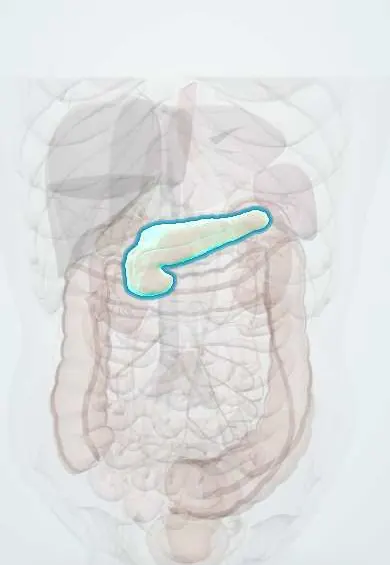
Structures involved
Tap one to see what it is and open it in 3D.
Why it happens
- Hyperplasia: physiologic and pathologic
- Gastric acid secretion
- Gastrointestinal hormones
- H⁺/K⁺-ATPase (gastric proton pump)
- Stomach: gastric glands, parietal and chief cells
- Enteroendocrine cells and GALT
What it is
A syndrome caused by a gastrin-secreting neuroendocrine tumour (gastrinoma), usually in the duodenum or pancreas. The excess gastrin causes marked acid hypersecretion with severe, multiple or atypical peptic ulcers, reflux and diarrhoea.
Who gets it
Rare; it accounts for a very small fraction of peptic ulcer disease. Most cases are sporadic, and about a quarter occur as part of multiple endocrine neoplasia type 1 (MEN1). Diagnosis is often delayed for years because acid-suppressing drugs mask symptoms.
Causes
- Gastrinoma: a neuroendocrine tumour that secretes gastrin
- Most arise in the 'gastrinoma triangle', in the duodenal wall or the head of the pancreas
- Sporadic tumours, or inherited as part of MEN1 (MEN1 gene)
- More than half are malignant, spreading to lymph nodes and liver
Risk factors
- Multiple endocrine neoplasia type 1 (with hyperparathyroidism and pituitary tumours)
- Family history of MEN1
Pathophysiology
Gastrin from the tumour stimulates parietal cells and their growth, so the stomach secretes very large amounts of acid. The acid overwhelms duodenal neutralisation, causing multiple ulcers, including in unusual sites such as the distal duodenum and jejunum. Acid in the small bowel inactivates pancreatic lipase and damages the mucosa, causing diarrhoea and fat malabsorption. Gastrin also thickens the gastric folds.
Classification
- Sporadic gastrinoma (most cases), often single
- MEN1-associated gastrinoma, usually multiple small duodenal tumours
- Localised versus metastatic (lymph nodes, liver)
Symptoms and signs
- Burning epigastric pain from peptic ulcers that are severe, multiple or recurrent
- Chronic watery or fatty diarrhoea that improves with acid suppression
- Severe gastro-oesophageal reflux
- Nausea, vomiting and weight loss
- Ulcers in atypical places (beyond the duodenal bulb, jejunum) or without Helicobacter pylori or NSAID use
Diagnosis
- Clinical
- Suspected with refractory, multiple or atypical ulcers, ulcers without H. pylori or NSAIDs, ulcers with diarrhoea, prominent gastric folds, or a personal or family history of MEN1.
- Tests
- Fasting serum gastrin is markedly raised while gastric pH is acidic (acid-suppressing drugs must be stopped carefully under supervision, since they also raise gastrin). A secretin stimulation test shows a paradoxical rise in gastrin. Serum calcium and parathyroid hormone screen for MEN1; chromogranin A may be raised.
- Imaging
- Upper endoscopy shows ulcers and thick gastric folds. Tumour localisation with contrast CT or MRI, somatostatin receptor imaging (gallium-68 DOTATATE PET/CT) and endoscopic ultrasound.
Differential diagnosis
- Common peptic ulcer disease from Helicobacter pylori or NSAIDs
- Other causes of high gastrin with low acid: atrophic gastritis, pernicious anaemia, acid-suppressing drugs
- Gastric outlet obstruction or G-cell hyperplasia
- Other causes of chronic diarrhoea (VIPoma, celiac disease, inflammatory bowel disease)
Goal of treatment
Control acid secretion to heal ulcers and prevent complications, then remove the tumour when possible and treat metastatic disease.
Treatment
- Medical
- High-dose proton pump inhibitors are the mainstay to control acid, heal ulcers and stop diarrhoea; somatostatin analogues for metastatic or unresectable tumours.
- Surgical
- Surgical exploration and removal of a localised sporadic gastrinoma can be curative; in MEN1 the decision is individualised, and parathyroid surgery for hyperparathyroidism is done first because high calcium increases gastrin.
- Medical
- For advanced disease: targeted therapies, chemotherapy, liver-directed treatments or peptide receptor radionuclide therapy.
- Follow-up
- Follow-up of gastrin levels, symptoms and imaging for recurrence; screening for other MEN1 tumours and genetic testing of relatives when MEN1 is present.
Drugs for this condition
Complications
- Ulcer bleeding, perforation and gastric outlet obstruction
- Oesophagitis and oesophageal stricture
- Malabsorption and weight loss
- Liver metastases
- Vitamin B12 deficiency with long-term acid suppression
Prognosis
Good when the tumour is localised and resected, and acid can usually be controlled with drugs. Survival depends mainly on the presence of liver metastases.
Test yourself
Think of the answer, then tap the question to see it.
Where is the 'gastrinoma triangle'?
The area bounded by the cystic duct–common bile duct junction, the junction of the second and third parts of the duodenum, and the neck–body junction of the pancreas; most gastrinomas lie in the duodenum or pancreatic head.
Which test shows a paradoxical rise in gastrin in Zollinger-Ellison syndrome?
The secretin stimulation test.
Which inherited syndrome is associated with gastrinoma?
Multiple endocrine neoplasia type 1 (parathyroid, pituitary and pancreatic tumours).
Why does Zollinger-Ellison syndrome cause diarrhoea?
Excess acid in the small bowel damages the mucosa and inactivates pancreatic enzymes, causing secretory and fatty diarrhoea.
What is the first-line drug class for controlling acid in gastrinoma?
Proton pump inhibitors, at high doses.
Related conditions
- Peptic ulcer disease
- Gastro-oesophageal reflux disease (GERD)
- Upper gastrointestinal bleeding
- Multiple endocrine neoplasia (MEN 1, 2A, 2B)
- Primary hyperparathyroidism
- Coeliac disease
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Zollinger-Ellison syndrome: MedlinePlus Medical Encyclopedia (MedlinePlus (U.S. National Library of Medicine), 2025).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.