Conditions · Pediatrics and neonatology
Child maltreatment (physical abuse, abusive head trauma, neglect) !
Child maltreatment is abuse or neglect of anyone under 18 by a caregiver. Health workers must recognise its signs and report it to protect the child.
Updated 2026-11-01
Structures involved
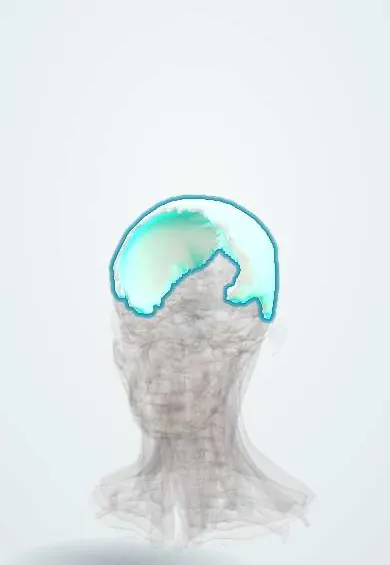
Tap one to see what it is and open it in 3D.
Why it happens
- Mechanical and electrical injury: abrasion, contusion, laceration, wounds
- Sudden infant death syndrome: what is known
What it is
Any abuse or neglect of a person under 18 years by a parent, caregiver or other person in a position of responsibility, trust or power that causes actual or potential harm to the child's health, survival, development or dignity. It includes physical, sexual and emotional abuse, neglect and exploitation.
Who gets it
Very common worldwide: WHO estimates that about 6 in 10 children under 5 regularly receive physical punishment or psychological violence at home, and 1 in 5 women and 1 in 7 men report sexual abuse in childhood. In Colombia, violence against children is a national public health priority; cases are notified to the public health surveillance system and to child-protection authorities, and under-reporting is common.
Causes
- Physical abuse: inflicted injury, such as hitting, shaking, burning or throwing
- Abusive head trauma (including shaken baby syndrome): violent shaking and/or blunt impact to an infant's head
- Neglect: failure to meet basic needs (food, hygiene, supervision, health care, schooling, emotional care)
- Emotional abuse and sexual abuse (covered in specific protocols)
Risk factors
- Child: age under 1 year (highest risk of severe and fatal injury), prematurity, disability or chronic illness, persistent crying
- Caregiver: young age, depression, substance use, own history of maltreatment, unrealistic expectations of the child
- Family: intimate partner violence, social isolation, poverty and stress
- Community: armed conflict and displacement, social norms that accept physical punishment
Pathophysiology
In abusive head trauma, acceleration-deceleration forces from shaking (with or without impact) tear bridging veins between the brain and dura, causing subdural haemorrhage, and shear the retina and brain tissue, causing multilayered retinal haemorrhages and diffuse brain injury with hypoxic-ischaemic swelling. Typical skeletal injuries come from squeezing the chest (posterior rib fractures) and pulling or twisting limbs (metaphyseal corner fractures). Chronic neglect causes growth failure and developmental delay.
Classification
- Physical abuse, including abusive head trauma
- Sexual abuse
- Emotional (psychological) abuse
- Neglect: physical, medical, educational, supervisory, emotional
- Exploitation (child labour, commercial sexual exploitation)
Symptoms and signs
- An injury that does not match the history, the child's developmental stage or a history that changes
- Delay in seeking care
- Bruises in non-mobile infants, or on the ears, neck, torso, buttocks or genitals; patterned bruises (hand, belt, cord)
- Patterned or immersion burns (glove-and-stocking, cigarette burns)
- Abusive head trauma in infants: irritability, vomiting, poor feeding, lethargy, seizures, apnoea, a bulging fontanelle or rapidly growing head
- Neglect: poor growth, poor hygiene, untreated illness or dental caries, missed vaccinations, developmental delay
- Behaviour changes: withdrawal, fear of caregivers, aggression, school problems
Diagnosis
- Clinical
- Careful, non-judgemental history recorded in the caregiver's own words, a full head-to-toe skin and genital examination, growth plotting and developmental assessment; precise documentation with body diagrams and photographs. Dilated fundus examination by an ophthalmologist in suspected abusive head trauma.
- Tests
- Complete blood count and coagulation studies to exclude bleeding disorders; liver enzymes, amylase and lipase and urinalysis to look for occult abdominal injury; calcium, phosphate, alkaline phosphatase and vitamin D when fractures are present; toxicology when indicated.
- Imaging
- Skeletal survey in children under 2 years with suspected physical abuse, often repeated after about 2 weeks; head CT acutely and brain MRI in suspected abusive head trauma; abdominal CT when liver enzymes are raised.
Differential diagnosis
- Accidental injury consistent with development and history
- Bleeding disorders (haemophilia, von Willebrand disease, vitamin K deficiency)
- Osteogenesis imperfecta and rickets
- Congenital dermal melanocytosis (blue-grey spots), cultural practices such as cupping or coining
- Glutaric aciduria type 1 or benign enlargement of subarachnoid spaces (for subdural collections)
Goal of treatment
Treat the injuries, make the child safe, and meet the legal duty to report; the clinician's role is to recognise, document and notify, not to investigate or prove guilt.
Treatment
- Acute
- Stabilise and treat injuries (airway, breathing, circulation, neurosurgical care for intracranial bleeding, fracture care).
- Procedure
- Report and notify: in most countries health workers have a legal duty to report reasonable suspicion to child-protection services. In Colombia the Code of Childhood and Adolescence (Law 1098 of 2006) makes the family, society and the State, health services included, co-responsible for protecting children and reporting maltreatment to the competent authorities (ICBF, family commissioners, police), and cases are also notified to public health surveillance. Reporting requires reasonable suspicion, not proof.
- Conservative
- Ensure a safe discharge plan, involving social work and the multidisciplinary child-protection team; protect siblings, who may also be at risk.
- Follow-up
- Nursing priorities: objective documentation using the caregiver's and child's own words, neurological observation, safe environment, calm supportive communication with the child, and follow-up of development and mental health.
Complications
- Death (abusive head trauma is a leading cause of fatal child abuse in infants)
- Permanent brain injury: epilepsy, cerebral palsy, intellectual disability, blindness
- Growth failure and developmental delay from neglect
- Post-traumatic stress, anxiety, depression, substance use and suicidal behaviour
- Cycle of violence across generations
Prognosis
Depends on the type and severity of abuse and on how early the child is protected. About 1 in 4 infants with abusive head trauma dies and most survivors have lasting disability; the psychological effects of all forms of maltreatment often persist into adulthood without support.
Prevention
- Home-visiting and parenting support programmes for high-risk families
- Education about normal infant crying (crying peaks around 6–8 weeks) and coping strategies: place the baby in a safe place and step away
- Recognising and acting on sentinel injuries
- Laws and social norms against physical punishment
Test yourself
Think of the answer, then tap the question to see it.
Which triad suggests abusive head trauma in an infant?
Subdural haemorrhage, multilayered retinal haemorrhages and encephalopathy (with or without fractures).
Which imaging study is recommended in a child under 2 years with suspected physical abuse?
A full skeletal survey (often repeated about 2 weeks later).
Which fractures are highly specific for physical abuse in infants?
Posterior rib fractures and classic metaphyseal (corner or bucket-handle) fractures.
Must a health worker prove abuse before reporting it?
No. A reasonable suspicion is enough; investigation belongs to child-protection and legal authorities.
What is a sentinel injury?
A minor injury, such as a bruise or mouth injury, in a young infant that may precede more severe abuse.
Related conditions
- Subdural haematoma
- Traumatic brain injury
- Rib fractures
- Osteogenesis imperfecta
- Epilepsy and seizures
- Cerebral palsy
- Sudden infant death syndrome (SIDS)
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Child maltreatment (World Health Organization, 2026); About Abusive Head Trauma (Centers for Disease Control and Prevention (CDC), 2026); Ley 1098 de 2006, Código de la Infancia y la Adolescencia (Congreso de la República de Colombia, 2006).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.