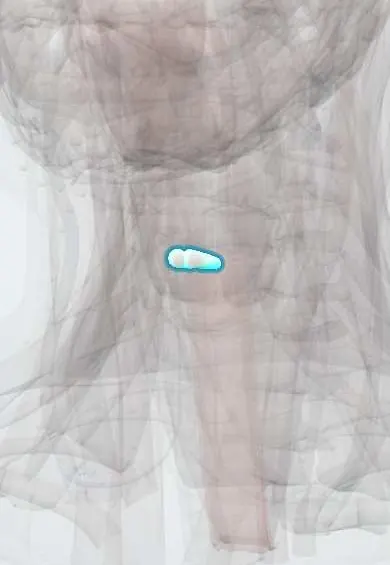
Laryngeal cancer !
Laryngeal cancer is a malignant tumour of the voice box; when it starts on the vocal cords it causes early, lasting hoarseness.
Updated 2026-10-29
Structures involved
Tap one to see what it is and open it in 3D.
- Vocal folds
- Thyroid cartilage
- Epiglottis
- Cricoid cartilage
- Arytenoid cartilages
- Neck lymph nodes
- Recurrent laryngeal nerves
- Trachea
Microorganisms that cause it
In histology
Why it happens
- Dysplasia and carcinoma in situ
- Tobacco: how smoking injures tissue
- Chemical carcinogens: initiation, promotion and the table to know
What it is
Malignant tumour of the larynx, almost always squamous cell carcinoma. It can arise above, at or below the vocal folds; glottic tumours cause early hoarseness and are often found at an early stage.
Who gets it
Mostly affects men over 50 with a history of smoking and alcohol use; rates in women have risen with smoking. One of the most common head and neck cancers.
Causes
- Squamous cell carcinoma (most cases)
- Tobacco smoking (main cause)
- Alcohol (synergistic with tobacco)
- Human papillomavirus (a minor role compared with the oropharynx)
- Occupational exposures (asbestos and others)
Risk factors
- Smoking
- Heavy alcohol use
- Male sex and older age
- Laryngopharyngeal reflux (association proposed)
- Leukoplakia or dysplasia of the vocal folds
- Occupational exposure to carcinogens
Pathophysiology
Carcinogens cause dysplasia of the laryngeal epithelium, progressing to carcinoma in situ and invasive cancer. The glottis has few lymphatics, so glottic tumours spread late to lymph nodes; supraglottic tumours have rich lymphatic drainage and often present with neck nodes. Growth can fix the vocal fold and invade cartilage.
Classification
- By site: supraglottic, glottic (most common), subglottic
- TNM staging (fixation of the vocal fold, cartilage invasion, neck nodes, distant spread)
Symptoms and signs
- Persistent hoarseness (early sign of glottic cancer)
- Sore throat or pain on swallowing
- Ear pain referred from the larynx
- Lump in the neck (lymph node)
- Difficulty swallowing
- Stridor and breathing difficulty in advanced disease
- Weight loss, coughing up blood
Diagnosis
- Clinical
- Laryngoscopy (flexible nasal endoscopy) shows the lesion and vocal fold movement. Examination of the neck looks for nodes.
- Tests
- Biopsy under direct laryngoscopy (microlaryngoscopy) confirms the diagnosis and maps the tumour; fine-needle aspiration of neck nodes.
- Imaging
- Contrast CT and/or MRI of the neck to stage the tumour, cartilage invasion and nodes; chest CT or PET-CT for distant spread and a second primary tumour.
Differential diagnosis
- Vocal fold nodules or polyps
- Chronic laryngitis and reflux laryngitis
- Leukoplakia without invasive cancer
- Laryngeal papillomatosis
- Vocal fold paralysis (from a lesion along the recurrent laryngeal nerve)
Goal of treatment
Cure the cancer while preserving the voice, swallowing and airway whenever possible; in advanced disease, control symptoms and quality of life.
Treatment
- Procedure
- Radiotherapy, organ-preserving, for early (stage I–II) disease, particularly glottic cancer.
- Surgical
- Transoral laser microsurgery or open partial laryngectomy for selected early tumours.
- Surgical
- Total laryngectomy with neck dissection for advanced disease with cartilage destruction, or for recurrence after radiotherapy; the patient breathes through a permanent tracheostoma.
- Medical
- Concurrent chemoradiotherapy (platinum-based) for larynx preservation in selected advanced cases; immunotherapy or other systemic therapy for recurrent or metastatic disease.
- Rehabilitation
- Voice rehabilitation after laryngectomy (tracheoesophageal prosthesis, electrolarynx, oesophageal speech) and swallowing therapy.
- Lifestyle
- Stopping smoking and alcohol, which improves treatment results and lowers the risk of a second cancer.
Complications
- Airway obstruction
- Loss of the natural voice after laryngectomy
- Swallowing problems and aspiration
- Treatment effects: dry mouth, fibrosis, hypothyroidism after neck radiation
- Second primary cancers (lung, head and neck)
Prognosis
Early glottic cancer has high cure rates. Prognosis worsens with nodal spread, supraglottic or subglottic site and advanced stage.
Prevention
- Not smoking and limiting alcohol
- Early laryngoscopy for persistent hoarseness
Test yourself
Think of the answer, then tap the question to see it.
What is the most common histological type of laryngeal cancer?
Squamous cell carcinoma.
Why do glottic cancers rarely spread to lymph nodes early?
The vocal folds have very sparse lymphatic drainage.
Which symptom lasting more than about 3 weeks in a smoker requires laryngoscopy?
Persistent hoarseness.
Which laryngeal cancers more often present with neck node metastases, supraglottic or glottic?
Supraglottic tumours, because the supraglottis has rich lymphatic drainage.
How does a patient breathe after total laryngectomy?
Through a permanent tracheostoma in the neck; the airway is separated from the mouth and nose.
Related conditions
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Laryngeal Cancer (StatPearls (NCBI Bookshelf), 2024).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.