Conditions · Ophthalmology and ENT
Vocal fold nodules, polyps and laryngitis !
Inflammation or small benign growths on the vocal folds that make the voice hoarse. Most are caused by voice overuse, infection, smoking or reflux.
Updated 2026-11-01
Structures involved
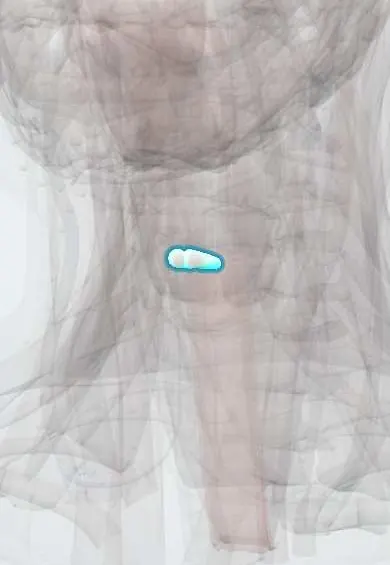
Tap one to see what it is and open it in 3D.
- Vocal folds
- Thyroid cartilage
- Arytenoid cartilages
- Thyroarytenoid
- Epiglottis
- Cricoid cartilage
- Superior laryngeal nerve
- Recurrent laryngeal nerves
- Trachea
- Pharynx
Why it happens
What it is
A group of common benign disorders of the vocal folds that cause hoarseness. Laryngitis is inflammation of the larynx, acute (usually viral) or chronic. Nodules are paired callus-like thickenings, and polyps are usually single, softer lesions; both form on the free edge of the folds and stop them from closing and vibrating evenly.
Who gets it
Hoarseness is one of the most frequent reasons to consult ENT. Acute viral laryngitis is very common in all ages. Nodules are typical of people who use their voice heavily for work, such as teachers, singers, call-centre staff and sales staff, a group often studied in Latin America, and of children who shout a lot (mostly boys). Polyps and smoker's polypoid swelling (Reinke oedema) are more frequent in adults who smoke.
Causes
- Acute laryngitis: viral upper respiratory infections; less often bacterial infection or vocal strain
- Chronic laryngitis: smoking, laryngopharyngeal reflux, inhaled irritants, chronic voice overuse, inhaled corticosteroids
- Nodules: repeated phonotrauma (shouting, singing or speaking loudly for long periods with poor technique)
- Polyps: a single episode of vocal trauma or chronic misuse, often with a small haemorrhage in the fold; smoking
- Reinke oedema: long-term smoking, sometimes with reflux or hypothyroidism
Risk factors
- Occupations with heavy voice use (teachers, singers, preachers, call-centre staff)
- Smoking and exposure to smoke, dust or chemical fumes
- Gastro-oesophageal and laryngopharyngeal reflux
- Frequent upper respiratory infections and allergic rhinitis with throat clearing
- Dehydration, alcohol and noisy work environments
- Anticoagulant or antiplatelet use (haemorrhagic polyps)
Pathophysiology
The vocal folds vibrate hundreds of times per second, and the impact stress is highest at the junction of their anterior and middle thirds. Repeated collisions injure the superficial lamina propria (Reinke space), which reacts with oedema and then fibrosis, forming bilateral nodules. A single forceful event can rupture small vessels and leave a unilateral polyp. Any mass or swelling on the edge prevents full closure and makes vibration irregular, so air escapes and the voice turns hoarse, breathy and tires quickly. In laryngitis the whole mucosa is inflamed and swollen.
Classification
- Acute laryngitis (less than 3 weeks), usually infectious
- Chronic laryngitis (more than 3 weeks): irritant, reflux-related, voice overuse
- Vocal fold nodules: bilateral, symmetrical, at the anterior-middle third junction
- Vocal fold polyps: usually unilateral, sessile or pedunculated, sometimes haemorrhagic
- Reinke oedema (polypoid corditis): diffuse swelling of both folds in smokers
Symptoms and signs
- Hoarseness or a rough, breathy voice; loss of voice (aphonia) in acute laryngitis
- Voice that tires through the day and loses range, especially high notes in singers
- Sore or scratchy throat, throat clearing and dry cough
- Feeling of a lump in the throat
- Fever, runny nose and swollen neck nodes when the cause is a viral infection
- Low-pitched voice in Reinke oedema
Diagnosis
- Clinical
- History of voice use, smoking, reflux, infection and duration. Listening to the voice and examining the neck. Hoarseness that persists beyond about 4 weeks, or sooner if red flags exist, should have the larynx visualised.
- Tests
- Laryngoscopy is the key test: flexible nasolaryngoscopy shows the folds directly, and videostroboscopy shows how the mucosal wave vibrates (useful to tell nodules from cysts). A voice assessment by a speech-language therapist. Biopsy only if a lesion looks suspicious.
- Imaging
- Not needed for nodules, polyps or simple laryngitis. CT of the neck if a malignant lesion or nerve paralysis is suspected.
Differential diagnosis
- Laryngeal cancer (squamous cell carcinoma)
- Vocal fold cyst or recurrent respiratory papillomatosis (HPV)
- Vocal fold paralysis
- Croup or epiglottitis in children
- Muscle tension dysphonia without a structural lesion
- Laryngeal tuberculosis or fungal laryngitis in immunosuppressed people
Goal of treatment
Restore a clear, functional voice, remove the cause of injury (overuse, smoke, reflux) and rule out cancer when hoarseness persists.
Treatment
- Conservative
- Relative voice rest, good hydration, humidified air and avoiding shouting, prolonged whispering and repeated throat clearing; acute viral laryngitis usually settles on its own in 1–2 weeks.
- Rehabilitation
- Voice therapy with a speech-language therapist (vocal hygiene and technique) is first-line for nodules and many polyps, and is also used before and after surgery.
- Medical
- Treat the cause: proton pump inhibitors and anti-reflux measures when laryngopharyngeal reflux is suspected, treatment of allergic rhinitis, and antibiotics only for proven bacterial infection.
- Lifestyle
- Stopping smoking and limiting alcohol and irritant exposure; this is essential in Reinke oedema and chronic laryngitis.
- Surgical
- Microlaryngeal surgery (phonomicrosurgery) to remove polyps, cysts or nodules that do not respond to voice therapy, followed by a short period of voice rest and therapy.
Complications
- Chronic dysphonia that limits work, with occupational and social impact
- Recurrence of nodules if voice habits do not change
- Scarring of the vocal fold after repeated injury or surgery
- Delayed diagnosis of laryngeal cancer when persistent hoarseness is not examined
- Airway obstruction in severe laryngitis in young children
Prognosis
Very good. Acute laryngitis resolves within days to a couple of weeks. Most nodules shrink with voice therapy; polyps often need surgery but rarely recur if the cause is controlled.
Prevention
- Vocal hygiene: hydration, rest periods and amplification for teachers and other voice professionals
- Not smoking and avoiding irritant fumes
- Controlling reflux and allergies
- Hand washing to limit respiratory infections
Test yourself
Think of the answer, then tap the question to see it.
Where on the vocal fold do nodules typically form, and are they unilateral or bilateral?
Bilaterally and symmetrically at the junction of the anterior and middle thirds of the free edge, where impact stress is greatest.
What is the first-line treatment for vocal fold nodules?
Voice therapy with a speech-language therapist and vocal hygiene; surgery is reserved for lesions that fail therapy.
A 60-year-old smoker has been hoarse for 6 weeks. What is the next step?
Laryngoscopy to visualise the vocal folds and exclude laryngeal cancer.
What is Reinke oedema and what is its main risk factor?
Diffuse swelling of the superficial lamina propria of both folds (polypoid corditis), giving a low-pitched voice; smoking is the main cause.
Do most cases of acute laryngitis need antibiotics?
No. Most are viral and settle with voice rest, hydration and humidification.
Related conditions
- Gastro-oesophageal reflux disease (GERD)
- Laryngeal cancer
- Vocal fold paralysis (recurrent laryngeal nerve injury)
- Croup (laryngotracheobronchitis)
- Acute epiglottitis
- Hypothyroidism
- Allergic rhinitis
- Human papillomavirus (HPV) infection
Educational information, not medical advice. For any symptom, see a health professional.
Sources: What Is Hoarseness? — Causes, Diagnosis & Disorders (National Institute on Deafness and Other Communication Disorders (NIDCD), 2026); Laryngitis (MedlinePlus, US National Library of Medicine, 2026).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.