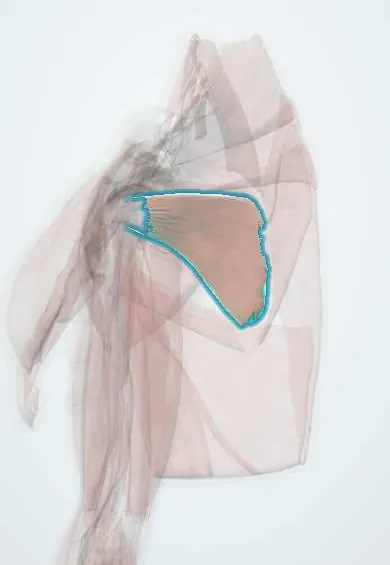
Subscapularis !
The subscapularis is the largest rotator cuff muscle, on the front of the shoulder blade against the ribs; it turns the arm inward and guards the joint.
Opens in the Durgical app, no sign-up needed.
What it is
The rotator cuff muscle on the front of the shoulder blade; it turns the arm inward.
What it does
Turns the arm inward and guards the front of the joint.
Key facts
- Origin
- Subscapular fossa
- Insertion
- Lesser tubercle
- Action
- Medially rotates and adducts the arm
- Nerve
- Upper and lower subscapular nerves (C5–C6)
- Blood supply
- Subscapular artery
Relations
- In front
- Serratus anterior across the scapulothoracic plane; the axillary contents, with the subscapular nerves and the thoracodorsal nerve running on its surface
- Behind
- Subscapular fossa of the scapula
- Above
- Coracoid process and the rotator interval; the subscapular bursa between its tendon and the neck of the scapula opens into the joint
- Below
- Teres major and latissimus dorsi; the axillary nerve and posterior circumflex humeral vessels pass below its lower border
- Lateral
- Anterior shoulder capsule and middle glenohumeral ligament, blended with the tendon; some fibres roof the intertubercular groove
How to find it
Mostly hidden against the front of the scapula. Part of the belly is reached in the posterior axillary fold with the arm abducted and relaxed, pressing toward the front of the scapula; the tendon lies lateral to the coracoid and moves under the fingers on rotating the arm.
Examination
- Lift-off test (Gerber): back of the hand on the lower back, lifting it away; inability points to a subscapularis tear (needs enough internal rotation to start)
- Belly-press test: hand pressed on the abdomen with the elbow kept forward; if the elbow drops back or the wrist bends, the subscapularis is weak; useful when the hand cannot reach the back
- Bear-hug test: hand on the opposite shoulder, resisting the examiner lifting it off; sensitive for upper-border tears
- More passive external rotation than on the other side suggests a large tear
On imaging
Axial MRI and ultrasound in external rotation show the tendon at the lesser tubercle; a long biceps tendon displaced medially out of its groove is an indirect sign of a subscapularis tear.
Common problems
- Rotator cuff tear, partial or full, from wear with age or from a fall; the most common cause of shoulder weakness.
- Tendinopathy and impingement: pain lifting the arm and at night.
- Calcific tendinitis: calcium deposits that cause sudden severe pain.
How it is diagnosed
Weakness and pain on cuff tests (for example the empty-can test). Ultrasound or MRI shows the tear size and muscle quality.
Treatment
- Physical therapy, pain medicines and sometimes injections, especially for partial and age-related tears.
- Arthroscopic rotator cuff repair with suture anchors for many full-thickness tears, especially recent ones in active people.
- Reverse shoulder replacement for large, irreparable tears with arthritis.
Clinical notes
- In the deltopectoral approach to the joint (replacement, stabilisation) it is detached and repaired; a failed repair shows as a positive lift-off or belly-press
- In the Latarjet procedure the coracoid graft passes through a split in the subscapularis, whose lower part then acts as a sling in front of the head
- The axillary nerve lies on its lower anterior surface and is at risk in anterior capsular surgery
Development
Although it lies on the front of the scapula, it develops from the dorsal muscle mass, so its upper and lower subscapular nerves branch from the posterior cord.
Memory aid
Rotator cuff 'SITS': Supraspinatus, Infraspinatus and Teres minor go to the greater tubercle; the last S, Subscapularis, is the odd one out on the lesser tubercle.
Related conditions
Test yourself
Think of the answer, then tap the question to see it.
Why is the subscapularis the main dynamic restraint against anterior shoulder dislocation?
It is the largest and strongest cuff muscle and the only one in front of the joint.
What are the attachments and nerve supply of the subscapularis?
From the subscapular fossa to the lesser tubercle; upper and lower subscapular nerves (C5–C6).
What are the lift-off and belly-press tests for the subscapularis?
Lift-off: inability to lift the back of the hand off the lower back. Belly-press: with the hand on the abdomen, the elbow drops back or the wrist bends.
Which nerve is at risk on the lower anterior surface of the subscapularis?
The axillary nerve, which runs across its front and dives below its lower border; at risk in anterior capsular surgery.
Educational information, not medical advice. For any symptom, see a health professional.
Its names
- Official Latin (TA2)
- musculus subscapularis TA2 2460
- Official Spanish (DeCS)
- Músculo subescapular
- English (TA2)
- Subscapularis
Related
Sources: Terminologia Anatomica (TA2); Anatomy, Shoulder and Upper Limb, Subscapularis Muscle; Anatomy, Rotator Cuff.
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.