Acute respiratory failure (hypoxaemic and hypercapnic) !
Acute respiratory failure is when the lungs suddenly cannot take in enough oxygen or remove enough carbon dioxide. It is a medical emergency.
Updated 2026-11-01
Structures involved
Tap one to see what it is and open it in 3D.
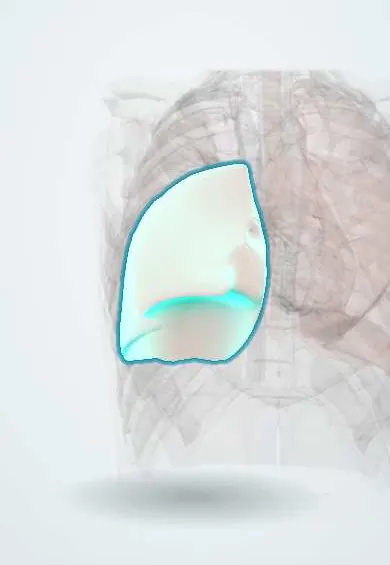
- Right lower lobe
- Left lower lobe
- Diaphragm
- Medulla oblongata
- Phrenic nerves
- Trachea
- Main bronchi
- Pleura
- External intercostals
In the clinical exam
- Respiratory rate and breathing patterns
- Pulse oximetry
- Chest inspection: shape, expansion, accessory muscles and retractions
- Respiratory distress and respiratory failure: the signs
Why it happens
- Hypoxemic and hypercapnic respiratory failure
- The causes of hypoxemia
- Ventilation–perfusion matching and West zones
- The alveolus: type I and II pneumocytes, surfactant, the blood–air barrier
What it is
A syndrome in which gas exchange fails over minutes to days, so arterial oxygen falls (hypoxaemic, type 1) and/or carbon dioxide rises (hypercapnic, type 2). It is defined by arterial blood gases, not by a single disease.
Who gets it
One of the most common reasons for admission to intensive care units worldwide and in Latin America. Pneumonia, sepsis, exacerbations of COPD and heart failure are the usual causes in adults; in Colombia, tuberculosis and high-altitude cities (where normal oxygen levels are lower) add to the context for interpreting gases.
Causes
- Hypoxaemic (type 1): pneumonia, ARDS, pulmonary oedema, pulmonary embolism, atelectasis, pneumothorax
- Hypercapnic (type 2) from the lungs or airways: COPD or severe asthma exacerbation, end-stage cystic fibrosis
- Hypercapnic from the respiratory centre: opioid or sedative overdose, stroke or injury of the brainstem
- Hypercapnic from nerves, muscles or chest wall: Guillain-Barré syndrome, myasthenic crisis, high spinal cord injury, flail chest, severe obesity
- Low inspired oxygen (high altitude) as a contributing factor
Risk factors
- Chronic lung disease (COPD, interstitial disease, cystic fibrosis)
- Neuromuscular disease or high spinal cord injury
- Use of opioids, benzodiazepines or other sedatives
- Older age, frailty and immunosuppression
- Major surgery, trauma or sepsis
Pathophysiology
Hypoxaemia comes mainly from ventilation-perfusion mismatch and shunt (alveoli filled with fluid or pus, or collapsed), with diffusion limitation and hypoventilation as other mechanisms; shunt responds poorly to extra oxygen. Hypercapnia comes from alveolar hypoventilation, because the drive, the pump (nerves, diaphragm, chest wall) or the load on the airways fails. Rising CO2 lowers blood pH (acute respiratory acidosis); in chronic CO2 retention the kidney retains bicarbonate to compensate.
Classification
- Type 1, hypoxaemic: PaO2 below about 60 mmHg with normal or low PaCO2
- Type 2, hypercapnic: PaCO2 above about 45–50 mmHg with acidaemia (pH below 7.35)
- Acute, chronic, or acute-on-chronic (e.g. COPD exacerbation)
- Perioperative (type 3) and shock-related (type 4) forms are sometimes added
Symptoms and signs
- Shortness of breath, fast breathing and use of accessory neck muscles
- Restlessness, anxiety or confusion from hypoxaemia
- Cyanosis of the lips and nail beds
- Tachycardia and sweating
- Headache, drowsiness, flushed warm skin and a flapping tremor (asterixis) when CO2 is high
- Paradoxical abdominal movement when the diaphragm tires
Diagnosis
- Clinical
- Rate, work of breathing, mental status and pulse oximetry at the bedside, then a search for the cause (history, chest examination, signs of heart failure, sepsis or overdose). Nursing priorities: airway, positioning upright, continuous oximetry and frequent reassessment.
- Tests
- Arterial blood gas is the key test: PaO2, PaCO2, pH and bicarbonate classify the type and whether it is acute or chronic; the alveolar-arterial gradient separates hypoventilation (normal gradient) from lung disease (raised gradient). Blood count, lactate, electrolytes, cultures, BNP or troponin and toxicology according to the suspected cause.
- Imaging
- Chest X-ray first; bedside lung ultrasound for pneumothorax, effusion, consolidation or B-lines of oedema; CT pulmonary angiography if pulmonary embolism is suspected; echocardiography for heart function.
Differential diagnosis
- Anxiety with hyperventilation (low CO2, normal oxygen)
- Metabolic acidosis with compensatory fast breathing (e.g. diabetic ketoacidosis)
- Severe anaemia or carbon monoxide poisoning (oximetry can be misleading)
- Upper airway obstruction (foreign body, angio-oedema)
- Cardiogenic shock with pulmonary oedema
Goal of treatment
Restore adequate oxygenation and ventilation quickly, protect the airway, and treat the underlying cause while avoiding complications of oxygen and mechanical ventilation.
Treatment
- Acute
- Controlled supplemental oxygen titrated to a target saturation, with a lower target in people at risk of CO2 retention (e.g. COPD); high-flow nasal oxygen in hypoxaemic failure.
- Procedure
- Non-invasive positive-pressure ventilation is first choice in hypercapnic COPD exacerbations and cardiogenic pulmonary oedema; intubation and invasive mechanical ventilation when it fails, consciousness falls or the airway is not protected.
- Medical
- Treatment of the cause: antibiotics for pneumonia or sepsis, bronchodilators and systemic corticosteroids for asthma or COPD, diuretics and vasodilators for pulmonary oedema, anticoagulation for pulmonary embolism, opioid antagonist for opioid overdose.
- Follow-up
- Continuous oximetry, repeated blood gases, capnography when ventilated, vital signs and level of consciousness; nursing care includes head-of-bed elevation, suctioning and ventilator-safety checks.
Drugs for this condition
Complications
- Cardiac arrest and hypoxic brain injury
- Arrhythmias and myocardial ischaemia
- Ventilator-associated pneumonia and ventilator-induced lung injury
- Barotrauma and pneumothorax
- ICU-acquired weakness, delirium and pressure injuries
Prognosis
Depends on the cause and on how fast it is reversed: drug overdose or pulmonary oedema often recover quickly, while ARDS, sepsis or advanced chronic lung disease carry substantial mortality. Survivors of long ICU stays may have lasting weakness and reduced quality of life.
Prevention
- Vaccination against influenza, pneumococcus and COVID-19 in people at risk
- Optimal control of COPD and asthma and stopping smoking
- Careful use and monitoring of opioids and sedatives
- Early mobilisation and breathing exercises after surgery
Test yourself
Think of the answer, then tap the question to see it.
How are type 1 and type 2 respiratory failure defined on blood gases?
Type 1 is hypoxaemia (PaO2 below about 60 mmHg) with normal or low PaCO2; type 2 is hypercapnia (PaCO2 above about 45–50 mmHg) with respiratory acidosis.
Which mechanism of hypoxaemia responds poorly to supplemental oxygen?
Shunt, where blood passes alveoli that are not ventilated (filled with fluid or collapsed), as in ARDS or lobar consolidation.
What does a normal alveolar-arterial gradient with hypoxaemia suggest?
Pure hypoventilation (e.g. opioid overdose or neuromuscular weakness) or low inspired oxygen, rather than lung disease.
In which situation is non-invasive ventilation the first-line support?
Hypercapnic respiratory acidosis in a COPD exacerbation, and also cardiogenic pulmonary oedema.
Which bedside signs suggest the patient is tiring and may need intubation?
Falling consciousness, a slowing respiratory rate or paradoxical abdominal breathing despite distress, and worsening acidosis on repeat gases.
Related conditions
- Acute respiratory distress syndrome (ARDS)
- Chronic obstructive pulmonary disease (COPD)
- Community-acquired pneumonia
- Hospital-acquired and ventilator-associated pneumonia
- Asthma
- Pulmonary embolism
- Pneumothorax
- Heart failure
- Sepsis and septic shock
- Guillain-Barré syndrome
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Respiratory Failure (National Heart, Lung, and Blood Institute (NHLBI, NIH), 2022).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.