
Idiopathic pulmonary fibrosis
A scarring lung disease of unknown cause in older adults that slowly stiffens the lungs, causing breathlessness and dry cough. Medicines can slow it down.
What it is
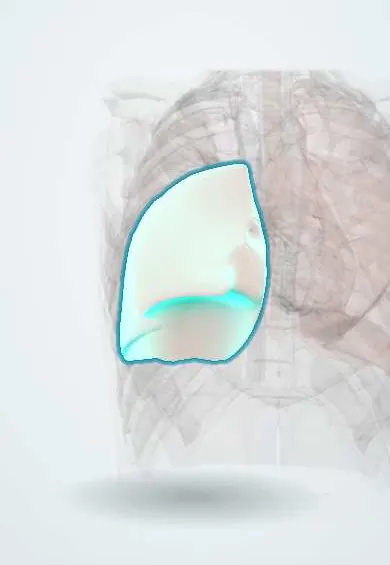
A chronic, progressive fibrosing interstitial pneumonia of unknown cause, limited to the lungs, defined by a usual interstitial pneumonia (UIP) pattern on high-resolution CT or biopsy once known causes of lung fibrosis have been excluded.
Who gets it
The most common idiopathic interstitial pneumonia. It mainly affects people over 60, more often men and former smokers; incidence rises steeply with age. Registry data from Latin America are limited, and many cases are diagnosed late or labelled as COPD or heart failure.
Causes
- Unknown by definition; thought to arise from repeated micro-injury of the alveolar epithelium in a susceptible, ageing lung
- Genetic susceptibility: MUC5B promoter variant, telomere-related gene mutations (TERT, TERC) and surfactant protein genes in familial cases
- Environmental triggers that add to risk: cigarette smoke, metal and wood dust, farming
- Possible contributors: chronic microaspiration from gastro-oesophageal reflux and viral infections
Risk factors
- Age over 60
- Male sex
- Current or past smoking
- Family history of pulmonary fibrosis
- Occupational exposure to metal, wood or stone dust
- Gastro-oesophageal reflux
Pathophysiology
Repeated micro-injury to type II alveolar cells (smoke, dust, reflux, ageing) in a susceptible lung (short telomeres, MUC5B variant) → the epithelium fails to regenerate and releases profibrotic signals, notably TGF-beta → fibroblasts turn into myofibroblasts, gather in fibroblastic foci and lay down collagen → the interstitium thickens, alveoli collapse and are replaced by honeycomb cysts lined by bronchiolar epithelium, starting in the subpleural lung bases → a stiff lung (restriction: low FVC and total lung capacity) with a lost diffusion surface (low DLCO) → hypoxaemia, first on exercise → chronic hypoxic vasoconstriction → pulmonary hypertension and cor pulmonale.
Classification
- HRCT pattern: UIP, probable UIP, indeterminate for UIP, or alternative diagnosis
- Course: slowly progressive (most), rapidly progressive, or with acute exacerbations
- Familial pulmonary fibrosis versus sporadic
- Severity by lung function: forced vital capacity (FVC) and DLCO, or the GAP index (gender, age, physiology)
Symptoms and signs
- Gradually worsening breathlessness on exertion over months to years
- Dry, persistent cough
- Fatigue and weight loss
- Fine, dry 'velcro' crackles at both lung bases
- Finger clubbing in about half of patients
- Late: cyanosis and signs of right heart failure (ankle swelling, raised neck veins)
Diagnosis
- Clinical
- Suspected in an older adult with chronic exertional breathlessness, cough and bibasal velcro crackles. A careful history excludes known causes: connective tissue disease, drugs, birds, moulds and occupational dusts. Diagnosis is made in a multidisciplinary discussion (pulmonologist, radiologist and, when needed, pathologist).
- Tests
- Spirometry and lung volumes show a restrictive pattern with reduced FVC and total lung capacity; DLCO is reduced, often early. The six-minute walk test shows exercise desaturation. Autoantibodies (antinuclear antibodies, rheumatoid factor, anti-CCP, myositis panel) look for connective tissue disease. Bronchoalveolar lavage or surgical or cryobiopsy only when imaging is not typical.
- Imaging
- High-resolution CT is central: a UIP pattern of subpleural, basal-predominant reticulation with honeycombing and traction bronchiectasis, often patchy, with little ground glass. A typical UIP pattern in the right clinical setting is enough for diagnosis without biopsy. Chest X-ray shows basal reticular shadows but can be normal early; echocardiography screens for pulmonary hypertension.
Differential diagnosis
- Connective tissue disease–associated interstitial lung disease
- Fibrotic hypersensitivity pneumonitis
- Asbestosis and other pneumoconioses
- Drug-induced pulmonary fibrosis
- Fibrotic nonspecific interstitial pneumonia
- Heart failure and COPD (common misdiagnoses)
Fibrosis on the CT: IPF or a look-alike?
| Condition | Clue in the history | CT pattern | Key test |
|---|---|---|---|
| Idiopathic pulmonary fibrosis | Man over 60, former smoker, no exposures or autoimmune signs | UIP: subpleural, basal honeycombing and traction bronchiectasis, little ground glass | Multidisciplinary diagnosis; biopsy only if the CT is not typical |
| Fibrotic hypersensitivity pneumonitis | Birds, feather bedding, moulds, damp housing | Upper- or mid-zone fibrosis with mosaic attenuation and air trapping on expiration | Exposure history; lymphocytosis on lavage |
| Connective tissue disease–associated ILD | Raynaud, arthritis, skin thickening, muscle weakness; often younger women | Usually NSIP (ground glass with subpleural sparing); UIP mainly in rheumatoid arthritis | Autoantibodies (antinuclear, anti-Scl-70, anti-CCP, myositis panel) |
| Asbestosis (pneumoconiosis) | Years of asbestos work: insulation, shipyards, brake linings | Basal UIP-like fibrosis with calcified pleural plaques | Occupational history; pleural plaques on CT |
| Heart failure | Orthopnoea, raised neck veins, leg oedema | Septal lines, effusions and ground glass that clear with diuretics | Natriuretic peptide and echocardiography |
Goal of treatment
Slow the loss of lung function with antifibrotic therapy, relieve symptoms, treat complications and comorbidities, and plan for transplantation or palliative care in time.
Treatment
- Medical
- Antifibrotic agents (pirfenidone or nintedanib) slow the yearly decline in FVC and are offered to most patients with confirmed IPF; common side effects are gastrointestinal upset and, with pirfenidone, photosensitivity rash.
- Medical
- Combination immunosuppression with prednisone, azathioprine and N-acetylcysteine is harmful in IPF and is avoided. Reflux is treated if symptomatic; cough and breathlessness may be eased with low-dose opioids in advanced disease.
- Rehabilitation
- Pulmonary rehabilitation, supplemental oxygen for resting or exertional hypoxaemia, vaccination against influenza, pneumococcus and COVID-19, and smoking cessation.
- Acute
- Acute exacerbation: hospital care, oxygen or high-flow nasal oxygen, exclusion of infection, heart failure and embolism; systemic corticosteroids are often used despite weak evidence. Invasive ventilation rarely helps and is discussed beforehand.
- Surgical
- Lung transplantation is the only treatment that prolongs survival substantially; suitable patients are referred early, at diagnosis or when function begins to fall.
- Follow-up
- Lung function (FVC, DLCO) and oxygen needs every few months; watch for pulmonary hypertension, lung cancer, sleep apnoea and depression; early advance care planning.
Complications
- Acute exacerbation with high short-term mortality
- Chronic respiratory failure
- Pulmonary hypertension and cor pulmonale
- Lung cancer
- Pneumothorax and pulmonary embolism
- Side effects of antifibrotic therapy (diarrhoea, weight loss, liver enzyme rise)
Common traps
- IPF is an inflammation, so corticosteroids help: it is faulty repair; prednisone with azathioprine and N-acetylcysteine increased deaths, and antifibrotics are the treatment
- A normal FEV1/FVC ratio means normal lungs: restriction keeps the ratio normal or high; look at FVC, total lung capacity and DLCO
- Breathlessness with crackles in an older former smoker is COPD or heart failure: fine bibasal velcro crackles with finger clubbing point to fibrosis; get a high-resolution CT
- Every UIP pattern is IPF: rheumatoid arthritis, asbestosis, chronic hypersensitivity pneumonitis and drugs also cause UIP; IPF is named only once they are excluded
- Antifibrotics restore lung function: they slow the yearly fall in FVC but do not undo scar; transplantation is the only treatment that substantially extends survival
Prognosis
Poor and variable: median survival without treatment is about three to five years from diagnosis. Antifibrotics slow decline, and transplantation can extend life in selected patients. A falling FVC or DLCO, low walking distance and acute exacerbations predict worse outcomes.
Test yourself
Think of the answer, then tap the question to see it.
Which HRCT pattern, if typical, allows a diagnosis of IPF without a biopsy?
Usual interstitial pneumonia: subpleural, basal-predominant reticulation with honeycombing and traction bronchiectasis, in a patient without another cause.
What is the classic lung sound on examination in IPF?
Fine, dry, end-inspiratory 'velcro' crackles at both lung bases.
Which two drug classes are used and avoided in IPF?
Antifibrotics (pirfenidone, nintedanib) slow decline; prednisone plus azathioprine plus N-acetylcysteine increased harm and is avoided.
What pattern do lung function tests typically show in IPF?
A restrictive pattern (low FVC and total lung capacity, normal or high FEV1/FVC ratio) with a reduced DLCO.
A 68-year-old ex-smoker: 18 months of exertional dyspnoea, velcro crackles, clubbing, FVC 62%, FEV1/FVC 0.86, DLCO 45%, no exposures or autoantibodies; CT: basal honeycombing. Biopsy?
No. This is IPF: restriction, low DLCO and a typical UIP pattern with known causes excluded is diagnostic after multidisciplinary review. Offer an antifibrotic and early transplant referral.
Why it happens
In anaesthesia
In rehabilitation
Connections
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Idiopathic Pulmonary Fibrosis (StatPearls (NCBI Bookshelf), 2024); Interstitial Pulmonary Fibrosis (StatPearls (NCBI Bookshelf), 2023).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.