
Arthritis as a clue to systemic disease
Sometimes sore or swollen joints are the first sign of a disease elsewhere, such as iron overload, sarcoidosis or a lung tumour. The joint pattern points to it.
What it is
Many systemic diseases first show in the joints: sarcoidosis (Löfgren syndrome), haemochromatosis, hyperparathyroidism and other causes of pyrophosphate deposition, hypothyroidism, acromegaly, haemophilia, sickle cell disease, HIV, amyloidosis and hypertrophic osteoarthropathy. The pattern leads to the diagnosis.
Who gets it
Varies by disease. Arthropathy occurs in about 45% of people with hereditary haemochromatosis. Löfgren syndrome is a common acute presentation of sarcoidosis, more frequent in people of European ancestry. In haemophilia, recurrent joint bleeding is the main cause of long-term disability. In sickle cell disease, dactylitis is common between six months and seven years of age, and osteonecrosis of the femoral head is a frequent adult problem.
Causes
- Granulomatous: sarcoidosis, including Löfgren syndrome (acute migratory polyarthritis, erythema nodosum, bilateral hilar adenopathy)
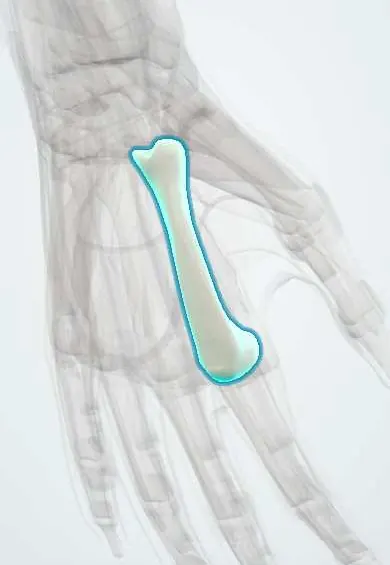
- Metabolic and crystal: hereditary haemochromatosis (2nd and 3rd MCP arthropathy, chondrocalcinosis); hyperparathyroidism, hypomagnesaemia and hypophosphatasia as causes of calcium pyrophosphate deposition
- Endocrine: acromegaly (cartilage overgrowth then degenerative arthritis), hypothyroidism (arthralgia, carpal tunnel, myopathy; true arthritis is rare)
- Haematological: haemophilia (haemarthrosis and haemophilic arthropathy), sickle cell disease (dactylitis, osteonecrosis, osteomyelitis and septic arthritis)
- Infectious and immune: HIV (HIV-associated arthritis, reactive and psoriatic arthritis; osteonecrosis and osteoporosis in the treatment era)
- Deposition: amyloidosis (carpal tunnel, trigger finger, shoulder and tendon disease; dialysis-related beta-2-microglobulin amyloid)
- Paraneoplastic and pulmonary: hypertrophic osteoarthropathy with clubbing and periostitis, most often from lung cancer
Risk factors
- Family history of haemochromatosis or haemophilia
- Long-term haemodialysis (beta-2-microglobulin amyloid)
- Heavy smoking or known lung disease (hypertrophic osteoarthropathy)
- Sickle cell disease, especially in children (dactylitis) and adults (osteonecrosis)
- Untreated HIV infection
- Young age at onset of crystal arthritis (suggests a metabolic cause)
Pathophysiology
Each disease reaches the joint by its own route. Iron deposits in synovium and cartilage and promotes calcium pyrophosphate crystals. High calcium, low magnesium or low alkaline phosphatase favour pyrophosphate crystal formation. Growth hormone excess makes cartilage overgrow and later break down. Repeated bleeding into a joint inflames the synovium, which bleeds more easily, destroying cartilage. Sickled cells block small vessels in bone, causing infarcts (dactylitis, osteonecrosis) that can become infected. Granulomas in sarcoidosis inflame periarticular tissue. Amyloid fibrils thicken tendons and the carpal tunnel. In hypertrophic osteoarthropathy, connective tissue proliferates in the fingertips and new bone forms along the long bones.
Classification
- Inflammatory clue: Löfgren syndrome, HIV-associated and reactive arthritis
- Degenerative-looking clue: haemochromatosis, acromegaly
- Crystal clue: calcium pyrophosphate disease from hyperparathyroidism, haemochromatosis, hypomagnesaemia, hypophosphatasia
- Bleeding or ischaemic clue: haemophilia, sickle cell disease
- Periarticular and soft-tissue clue: amyloidosis, hypothyroidism, hypertrophic osteoarthropathy
Symptoms and signs
- Ankle swelling with red tender shin nodules and fever (Löfgren syndrome)
- Stiff, bony 2nd and 3rd knuckles in a middle-aged person (haemochromatosis)
- Acute hot knee or wrist in a younger person with crystal arthritis (calcium pyrophosphate from a metabolic cause)
- Larger rings, gloves and shoes with joint pain (acromegaly)
- Acute painful swollen knee, elbow or ankle after minimal trauma (haemophilia)
- Painful swollen hands and feet in a young child, or groin pain in an adult (sickle cell disease)
- Clubbed fingers with aching shins or forearms (hypertrophic osteoarthropathy)
- Numb fingers at night from carpal tunnel syndrome (amyloid, hypothyroidism, acromegaly)
Diagnosis
- Clinical
- Ask what does not fit the common arthritides: the joint (2nd and 3rd MCP, ankles, carpal tunnel), the age (crystal arthritis before old age) or a sign beyond the joints (clubbing, erythema nodosum, skin pigmentation, enlarged hands, a bleeding history, anaemia). Examine the skin, nails, chest and lymph nodes.
- Tests
- Choose by suspicion. Iron studies (ferritin, transferrin saturation) and HFE genotyping for haemochromatosis. Serum calcium, parathyroid hormone, magnesium, alkaline phosphatase and iron studies in younger patients with calcium pyrophosphate disease; joint fluid shows rhomboid, weakly positively birefringent crystals. IGF-1 and a glucose growth-hormone suppression test for acromegaly. TSH for hypothyroidism (creatine kinase may be raised). Clotting studies and factor assays for haemophilia. HIV test in new reactive or unexplained inflammatory arthritis. Serum calcium and ACE are supportive in sarcoidosis. Fat aspirate or organ biopsy with Congo red staining for amyloid.
- Imaging
- Hand radiographs: hook-like osteophytes at the 2nd and 3rd MCP and chondrocalcinosis (haemochromatosis); tufting of terminal phalanges (acromegaly). Chest X-ray or CT: bilateral hilar adenopathy (Löfgren syndrome) or a lung mass (hypertrophic osteoarthropathy, with periostitis on long-bone films). MRI for early femoral head osteonecrosis in sickle cell disease or HIV.
Differential diagnosis
- Primary osteoarthritis (spares the MCP joints, older age)
- Rheumatoid arthritis (symmetric small-joint synovitis, positive serology)
- Gout and primary calcium pyrophosphate disease of old age
- Spondyloarthritis (psoriatic, reactive, enteropathic)
- Septic arthritis
- Polymyalgia rheumatica (versus hypothyroid myopathy)
The joint points to the disease
| Disease | Joint signature | Clue outside the joint | Key test |
|---|---|---|---|
| Sarcoidosis (Löfgren) | Acute migratory polyarthritis, mainly ankles | Erythema nodosum, fever, bilateral hilar nodes | Chest X-ray |
| Haemochromatosis | 2nd and 3rd MCP, osteoarthritis-like, chondrocalcinosis | Diabetes, liver disease, skin bronzing, hypogonadism | Ferritin and transferrin saturation |
| Hyperparathyroidism | Calcium pyrophosphate arthritis (knee, wrist) | High calcium, kidney stones | Calcium and parathyroid hormone |
| Acromegaly | Early cartilage overgrowth, later degenerative arthritis | Enlarging hands, feet and jaw | IGF-1 |
| Hypothyroidism | Arthralgia, carpal tunnel; true arthritis rare | Fatigue, cold intolerance, myopathy | TSH |
| Haemophilia | Recurrent haemarthrosis of knee, elbow, ankle | Male, bleeding history | Factor VIII or IX levels |
| Sickle cell disease | Dactylitis in children; femoral head osteonecrosis | Anaemia, pain crises | Haemoglobin electrophoresis |
| HIV | Reactive or psoriatic-type arthritis; osteonecrosis | Risk history, other infections | HIV test |
| Amyloidosis | Carpal tunnel, trigger finger, shoulder and tendon disease | Macroglossia, heart failure, neuropathy | Fat aspirate with Congo red |
| Hypertrophic osteoarthropathy | Aching long bones and joints, periostitis | Finger clubbing | Chest imaging for lung cancer |
Goal of treatment
Find and treat the underlying disease, relieve joint symptoms safely for that disease, and prevent irreversible joint damage.
Treatment
- Medical
- Treat the cause: phlebotomy for haemochromatosis, correction of hyperparathyroidism or hypomagnesaemia, control of growth hormone excess, thyroid hormone replacement, antiretroviral therapy for HIV, and treatment of the tumour in hypertrophic osteoarthropathy.
- Acute
- Haemophilic joint bleed: immediate replacement of the missing clotting factor (or a non-factor agent in haemophilia A), even before tests are complete; avoid aspirin, NSAIDs and intramuscular injections.
- Medical
- Symptomatic relief chosen for the disease: NSAIDs for Löfgren syndrome, which is usually self-limiting; treatment of calcium pyrophosphate flares; carpal tunnel release when needed.
- Surgical
- Joint replacement for advanced osteonecrosis (sickle cell disease, HIV) or destroyed joints (haemophilic arthropathy), with specialist perioperative haematology support.
- Follow-up
- Follow-up of the systemic disease (iron indices, calcium, IGF-1, factor levels, chest imaging) and of joint function; nurses teach early recognition of joint bleeds and sickle cell infections.
Complications
- Missed diagnosis of a treatable or dangerous disease (iron overload with cirrhosis, lung cancer, amyloid heart disease)
- Chronic synovitis and joint destruction after repeated haemarthrosis
- Femoral head collapse from osteonecrosis
- Septic arthritis and osteomyelitis in sickle cell disease
- Disability from progressive degenerative arthritis in acromegaly
Common traps
- Bony 2nd and 3rd knuckles are just osteoarthritis: primary osteoarthritis rarely targets the MCP joints, so check iron studies.
- Calcium pyrophosphate arthritis is simply a disease of old age: in younger patients look for hyperparathyroidism, haemochromatosis and hypomagnesaemia.
- Löfgren syndrome needs strong immunosuppression: it is usually self-limiting and settles with symptomatic treatment.
- A hot swollen knee in haemophilia should be aspirated first: replace the missing factor at once; bleeding is the cause until shown otherwise.
- Clubbing with aching shins is a rheumatological problem: hypertrophic osteoarthropathy is often paraneoplastic, so image the chest.
Prognosis
Depends on the underlying disease and how early it is found. Löfgren syndrome has an excellent prognosis and rarely relapses. Joint damage from haemophilia and haemochromatosis is often permanent once established, which is why early recognition matters. Hypertrophic osteoarthropathy may improve when the underlying tumour is treated.
Prevention
- Family screening for haemochromatosis and haemophilia
- Factor prophylaxis programmes in haemophilia to prevent joint bleeds
- Early metabolic work-up of crystal arthritis in younger patients
- Stopping smoking
Test yourself
Think of the answer, then tap the question to see it.
Which joints are characteristically affected in haemochromatosis arthropathy?
The 2nd and 3rd metacarpophalangeal joints, with an osteoarthritis-like picture and often chondrocalcinosis.
What triad defines Löfgren syndrome?
Acute migratory polyarthritis (classically the ankles), erythema nodosum and bilateral hilar adenopathy, often with fever.
Which tests are suggested in a younger patient with calcium pyrophosphate arthritis?
Serum calcium, parathyroid hormone, magnesium, alkaline phosphatase and iron studies.
A smoker has finger clubbing and aching shins with periostitis on X-ray. What must be looked for?
Lung cancer, the most common cause of hypertrophic osteoarthropathy with clubbing.
Which musculoskeletal problem in amyloidosis can appear years before heart involvement?
Carpal tunnel syndrome, along with trigger finger, biceps tendon rupture or spinal stenosis, mainly in wild-type transthyretin amyloid.
Connections
Educational information, not medical advice. For any symptom, see a health professional.
Sources: Hereditary Hemochromatosis - Hematology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Sarcoidosis - Pulmonology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Calcium Pyrophosphate Deposition Disease - Rheumatology and Orthopedics - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Gigantism and Acromegaly - Endocrinology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Hypothyroidism - Endocrinology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Hemophilia - Hematology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Amyloidosis - Hematology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Evaluation of the Patient With Pulmonary Issues - Pulmonology - MSD Manual Professional Edition (MSD Manual Professional Edition, 2025); Musculoskeletal Manifestations of Sickle Cell Disease: A Review (Cureus, 2015); Human immunodeficiency virus infection (HIV)–associated rheumatic manifestations in the pre- and post-HAART eras (Clinical Rheumatology, 2020).
Spotted a mistake?We are always improving for the community. Tell us what is wrong and our team will review it.Report a mistake
Representative model, for educational purposes only.